Monday, July 25, 2022

Ankle fracture Maisonneuve Fracture – Everything You Need to Know


      Ankle fracture Maisonneuve Fracture – Everything You Need to Know


                         https://www.youtube.com/watch?v=m35lMOtMJHQ

Maisonneuve fracture involves fracture of the proximal fibula associated with an occult and unstable injury of the ankle. The problem in these patients occur when the ankle injury is presented without a fracture of the lateral malleolus, or the medial malleolus and the injury is mistakenly diagnosed as an ankle sprain and the proximal fibular fracture is missed. Examine the leg for tenderness in the proximal fibula to diagnose a proximal fibula fracture. The patient could be mistakenly treated for having an isolated proximal fibular fracture alone and the ankle injury is missed.

 High index of suspicion is necessary to diagnose and treat this injury. Maisonneuve fracture equals syndesmotic injury. Syndesmotic Injury equals Syndesmotic Reduction and Fixation. If ankle x-rays show medial or posterior malleolus fracture, or a medial clear space widening with no fracture of the lateral malleolus, then you must obtain a long-leg films to assess possible proximal fibular fracture. Clinical examination of their entire leg for pain and tenderness in addition to long leg films of the entire leg that includes the ankle, and the knee is mandatory in case of the patient with approximate fibular fracture to exclude the presence of an additional ankle injury, or if the patient has an unexplained increase in the medial clear space of the ankle joint. You should be searching for the presence of a high fibular fracture. Look for signs of syndesmotic injury such as an unexplained increase in medial clear space or tibiofibular clear space is widened and it should be less than 5 millimeters.

So how do you explain this injury? It is explained by the presence of rotation force to the ankle with transmission of the force through the interosseous membrane, which exits through a proximal fibular fracture. Maisonneuve fracture occurs from external rotation of the foot, most often with pronation mechanism. This force has to go somewhere! If you don't see a fracture of the fibula then do the squeeze test or the external rotation stress test (both will show syndesmotic). The injury can involve the deltoid ligament injury or medial malleolar fracture medially and a fibular fracture proximally. Additionally, the tibiofibular ligaments are also involved, which can be the anterior tibiofibular ligament, interosseous ligament, the posterior tibiofibular ligament or posterior malleolar fracture. This looks like a very unstable ankle injury that may not be very obvious at presentation and you have to look out for it.

So how do you treat an Maisonneuve Fracture? This treated by fixation of the tibiofibular syndesmotic injury (key of treatment) or syndesmotic screws. if you have a medial site injury and there is a tear of the deltoid ligament, leave it alone. if there's a medial malleolus fracture you should fix that of the lateral side if there's approximate fibular fracture leave it alone. If there is a medial malleolar fracture, it should be fixed. If there is a proximal fibular fracture on the lateral side, leave it alone. As for the Syndesmotic Injury, the fixation has to be stable and adequate. Because of the magnitude of the injury, the Maisonneuve fracture may require more syndesmotic screws than with a routine ankle fracture with syndesmotic injury. After the fixation you will give a short leg non-weight bearing splint for six to eight weeks. Here is a patient taste example: the proximal fibular fracture and you can see increase in the medial clear space and you can see that the syndesmosis is widened. You can see that in the posterior malleolar fracture the patient is fixed with syndesmotic screws.

Thursday, July 14, 2022


The ideal Patient with Low Back Pain – Everything you need to know

https://www.youtube.com/watch?v=RW4uQvil0L8


Low back pain is very common, and the majority of the patients get better with time. The ideal patient will get better with time and has no radiation below the knee, no history of trauma, no fever or chills or weight loss, no bladder or bowel dysfunction, no neurological deficits, and no pathological reflexes.

In order to optimize recovery, management of the patient should consist of early return to activity as tolerated, as the symptoms allow. You will give the patient reassurance with limited analgesia, early range of motion, and muscle relaxants. A healthy patient with an acute onset of non-traumatic low back pain, you do not need early diagnostic imaging before proceeding with the therapeutic treatment. Diagnostic imaging is not necessary unless the initial treatment is unsuccessful, and the symptoms are prolonged. X-rays may not be needed in the first six weeks unless there is a reason for it, such as red flags. In fact, the use of x-rays can lead to better patient satisfaction but doesn’t necessarily lead to better patient outcome. X-rays and MRIs may show changes in the intervertebral discs and may be associated with the patient’s pain, but these changes are also commonly seen in cross-sectional studies of asymptomatic people. There are a lot of false positive MRIs, and you need to correlate the MRI findings with the clinical findings. Don't rely on the MRI alone! Just because you have MRI changes or disc protrusion, it does not mean that the patient needs surgery!

A nonspecific pain does not require surgery; therefore, it does not require further work-up. There are risk factors associated with low back pain that includes Poor physical fitness; Smoking; History of repetitive bending or stooping on the job and whole-body vibration exposure. If the patient has a simple low back pain, 50% of the patients resolve their pain in one week. Resolution of the acute back pain occurs in 90% of the patients within one month. If the patient has leg pain greater than back pain, then the patient has sciatica. Sciatica means nerve root irritation, probably due to a herniated disc.

Tuesday, January 18, 2022

Frozen Shoulder Adhesive Capsulitis - Everything You Need To Know

Frozen Shoulder Adhesive Capsulitis - Everything You Need To Know

https://www.youtube.com/watch?v=VhfaPe8f7g0 

Frozen shoulder (adhesive capsulitis)

The frozen shoulder can be associated with diabetes or thyroid disease.  It may be the initial presenting symptom for these conditions.  The exact details of this relationship remain poorly understood.  Ever patient with a frozen shoulder should have the HbA1c and TSH levels tested.  Also, check for arthritis, rheumatoid factors and antinuclear antibodies.  Most patients with frozen shoulder are female between the ages of 40 and 60 years old.  And frozen shoulder, the patient will lose both the active and the passive range of motion of the shoulder.  The patient develops pain, which means that there is inflammation with early fibrosis of the joint capsule, leading to joint stiffness.  The active and passive global motion, especially external rotation, will be reduced compared to the other side.  The shoulder pain and motion loss is usually not related to trauma.  It is an idiopathic process that results in shoulder pain and loss of motion due to contracture of the capsule.  The essential lesion involves the coracohumeral ligament and the rotator interval.  The synovial inflammation and capsular fibrosis results in pain and joint volume loss.  Check for previous trauma or fractures.  Rule out shoulder joint arthritis and rule out posterior dislocation of the shoulder.  It can also occur post-surgery from a rotator cuff tear.  It may also be associated with dupuytren disease and cervical disc disease.  Check for medical comorbidities such as stroke or cardiac diseases.  The x-ray will exclude trauma, malignancy, arthritis, calcific tendinitis, impingement, and AC joint arthritis.  And frozen shoulder, the humeral head will remain in its normal location.


MRI

There is a space reduction in the axillary recess.  Rotator cuff strength is normal by exam and on the MRI.  The pain and stiffness lasts beyond 6 months, then you can do manipulation of the shoulder under anesthesia.  There is a 50% failure rate in diabetics.  The diabetes is associated with a much worse prognosis and poor outcome for surgical and nonsurgical treatment.


Treatment

·         Nonoperative

o   This should be done for at least 3 to 6 months.

o   Supervised or home-based capsular stretching program +/-intra-articular steroid joint injection.

o   Nonsteroidal anti-inflammatory medication

·         Surgery

o   Capsular release (arthroscopic or open) and release the intra-articular and subacromial adhesions.

o   The axillary nerve may be injured during release of the capsule.

o   Utilize surgery in patients that have failure of initial conservative treatment for 3 months, and the patient remains functionally limited.


Monday, January 10, 2022

Ankle Arthritis - Everything You Need to Know

Ankle Arthritis - Everything You Need To Know - Dr. Nabil Ebraheim

https://www.youtube.com/watch?v=ysx-FT6fllA

The patient will have longstanding global pain that is inside the ankle.  The patient will have antalgic gait with swelling of the ankle and decreased ankle motion.  You want to check the sensation.  Lack of sensation with Simmons–Weinstein 5.07 monofilament testing is important because insensate patients are poor candidates for ankle joint replacement.  The patient will usually have a trial of nonsurgical treatment first.
Treatment

  •          Anti-inflammatory medication
  •         Activity modification
  •         Ankle orthosis/bracing
  •          Injections


Treatment Orthosis

·       Single rocker sole shoe modification and custom Arizona brace.  You may give the patient a cane.

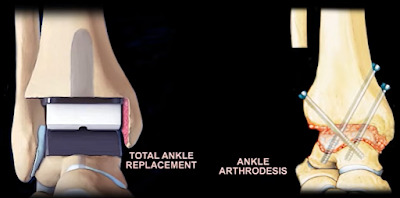
With failed conservative treatment, the patient may need arthrodesis of the ankle, which is fusion of the ankle, or an ankle replacement.  If you are going to do arthrodesis of the ankle, it will be arthrodesis of the tibiotalar joint.  In ankle arthrodesis, the fixation can be done by multiple techniques.  The whole idea is to obtain rigid fixation.  You can use plates, screws, or combination of both.

How to you position arthrodesis?

·         Neutral flexion

·         The gastroc recession or TAL may be needed if we cannot achieve neutral dorsiflexion.  From 0–5 hindfoot valgus when 5–10 external rotation of the foot.


Arthrodesis

·         80% will have difficulty on even ground.

·         75% will have difficulty with stairs.

If you find a person with an ankle fusion that when they walk, they have knee hyperextension when the heel comes off the ground during the stance phase, then that person's ankle is fused and some plantar flexion.  The plantar flexion position will create forced recurvatum of the knee.  The ankle should be fused in neutral flexion.  If the person has arthritis of the ankle joint and the subtalar joint, then you will do tibiocalcaneal arthrodesis.  Some people elect to go for total ankle replacement.


What are the contraindications for total ankle replacement?

  •  Severe deformity
  • Charcot joint
  • Avascular necrosis of the talus
  • Soft tissue compromise
  • Active ankle infection


What is the relative contraindication for ankle joint replacement?

  • Ligament instability
  • Diabetes
  •  Smoking
  •  Osteoporosis
  • Morbid obesity


When do you do distraction arthroplasty?

            You do this in younger patients with some motion and less severe joint destruction.


Arthritis of the ankle can be osteoarthritis, posttraumatic arthritis, or inflammatory arthritis as rheumatoid arthritis or gout.  Posttraumatic arthritis accounts for 80% of all ankle arthritis.  The primary osteoarthritis is about 10% only.  Pain with weightbearing, swelling, decreased range of motion compared to the other side, and you will be able to see the arthritis on the x-ray.  Ankle arthrodesis will be done in younger patients with a high demand, or if the patient has comorbidities such as diabetes and obesity.  10 years after ankle arthrodesis, 50% of the patients will have subtalar arthritis.  Some of the patients may get nonunion. Revision of the nonunion can lead to fusion in about 85%.  A young, active worker is a contraindication to total ankle arthroplasty.  You will do the arthrodesis and end-stage ankle arthritis and the union rate is about 90%.  The arthrodesis gives us a reliable pain control but will also give us adjacent joint arthritis.  The entire foot and the patient's comorbidities must be evaluated to choose the proper surgical technique.  Total ankle arthroplasty has superior gait mechanics compared to ankle arthrodesis.  Ankle arthrodesis is done 6 times more than a total ankle replacement.  If you have an elderly patient with no comorbidities and you want to do a motion preserving procedure, then this would be total ankle arthroplasty.  Revision of total ankle occurs due to loosening of the implant or subsidence, especially in patients less than 55 years old.  In a patient with rheumatoid arthritis with end-stage arthritis, total ankle may be a reasonable option.  In older patients with low demand, you will give total ankle arthroplasty.  In younger, active patients he will do a fusion.  The total ankle arthroplasty is gaining a lot of popularity.  For patients with nonunion, you need to evaluate for infection and metabolic bone disease.  You may also need a CT scan.  Preservation of the fibula can help the potential conversion to a total ankle at a later date.  When you compare patient with an ankle prosthesis to a patient with thin ankle fusion, there is more complication rate and revision rate for a patient with total ankle and more increased wound complications for people with rheumatoid arthritis.  If you are in doubt, use ankle arthrodesis.


Monday, January 3, 2022

Differential Diagnosis Of Spinal Stenosis

Written by: Vihan DeSilva with Dr. Nabil Ebraheim

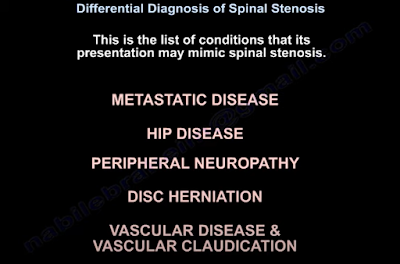
Spinal stenosis is a diagnosis mainly made through history and CT/MRI imaging as physical exam findings can be normal namely in lumbar spinal stenoses. A common finding along with painful extension of the spine and decreased lumbar lordosis is narrowing of the spinal foramina, but diagnosis is made when patients present with neurogenic claudication and/or cervical myelopathy. The cause may be congenital or acquired through, for example, endocrinopathies, calcium metabolism disorders, inflammatory diseases, and infectious diseases.1,2 There are other diseases that produce similar symptoms that should be considered in the differential diagnosis of spinal stenosis including metastatic disease, hip disease, peripheral neuropathy, disc herniation, and vascular disease/ vascular claudication.2 The rest of this article will be a discussion on how to differentiate spinal stenosis from these other conditions.


Patients’ pain may be metastatic if it is constant and worse at night or is unresolved even after previous attempts at treatment. Metastatic origin of pain should also be considered in patients who have a cancer/ cancer treatment history or experience fatigue, malaise, unintentional weight loss, or nonspecific symptoms.2,3

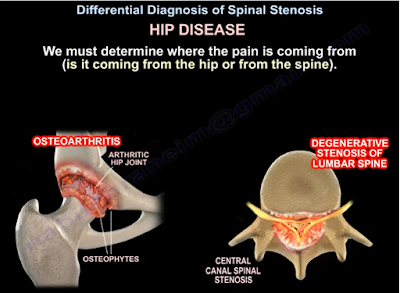
Distinguishing hip disease (ie. osteoarthritis) pain from lumbar stenosis pain can be challenging because the two ailments can coexist in a condition known as hip-spine syndrome. The location of the pain can be helpful in identifying the primary pain generator: hip pain can be felt in the groin, lateral hip, posterior hip, or near the spine and SI joint. Internal rotation of the hip can also be compromised in hip disease.2,4 Another way to isolate the pain generator is to inject the hip with steroid and observe. Worsening symptoms could indicate pain coming from lumbar stenosis. However, increased activity of the patient may also cause pain in related structures after the initial injection if it was successful in treating pain from underlying hip osteoarthritis.2

Peripheral neuropathy can also coexist with lumbar stenosis and may further complicate the differential diagnosis of spinal stenosis. EMG studies could aid in discerning stenosis from peripheral neuropathy and motor neuron disease.5 Certain clinical findings may also be useful. Bilateral burning foot pain at night is a distinguishing feature of peripheral neuropathy whereas unilateral leg pain with activity that is relieved by sitting is characteristic of lumbar stenosis/ radiculopathy. Additionally, sensory testing that demonstrates a dermatomal pattern indicates a problem in the spinal root whereas a glove and stock pattern would hint towards peripheral neuropathy.1,2

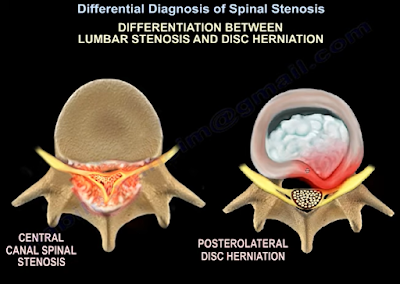
Disc herniation should also be considered against spinal stenosis as a possible source of pain. Location of pain can once again help in identifying the correct source. According to one comparative study, herniations tend to produce leg pain in the anterior thigh, anterior knee, and shin whereas posterior knee pain was common with stenosis.6 Furthermore, characteristics of stenosis include bilateral, nonspecific leg pain that is generally above the knee and rarely produces a positive straight-leg test. In contrast, herniation causes unilateral pain along the dermatome of the affected nerve root along with a positive straight-leg test.2

Vascular disease should be ruled out as well when considering a spinal stenosis diagnosis. One main distinguishing principle is that vascular disease produces vascular claudication whereas spinal stenosis produces neurogenic claudication. These two different types of claudication have different clinical sequelae. For instance, the distance a patient can walk before feeling symptoms is more variable with neurogenic claudication than with vascular claudication and uphill walking is better tolerated only with neurogenic claudication. Sitting attenuates neurogenic claudication symptoms whereas both sitting and standing still may ease vascular claudication symptoms.7 Vascular pain travels from distal sites to proximal ones whereas neurogenic pain goes from proximal to distal. Unlike vascular claudication, bilateral pedal pulses are normal with neurogenic claudication. Unlike spinal stenosis, vascular disease may produce lower extremity ulcers, hair loss, edema, and skin changes.2 Lastly, postural adjustments, such as flexion of the spine, ease stenosis claudication symptoms due to relief of pressure on the nerve roots. This is not true in vascular disease. This is also why a bicycle test relieves stenosis pain while making vascular pain worse.8

                Other rarer considerations include spinal arteriovenous malformations, tumors of the cauda equina, and differential diagnosis of myelopathy (ALS, multiple sclerosis, or subacute combined degeneration).1 Once a spinal stenosis diagnosis is made, the condition can be managed non-surgically with drugs, physiotherapy, and injections or surgically through decompression, spinal fusion, or interspinous spacer devices.9 Evidence is still being gathered on effectiveness and outcomes for all these non-surgical and surgical treatment options though.


References

1. Melancia JL, Francisco AF, Antunes JL. Spinal stenosis. Handb Clin Neurol. 2014;119:541-9.

2. Ebraheim N. Differential Diagnosis of Spinal Stenosis [Internet]. Toledo (OH): University of Toledo Medical Center, Department of Orthopedic Surgery; 2021 Jun 25. Available from: https://www.youtube.com/watch?v=eYxPmrnfjfA&ab_channel=nabilebraheim.

3. Dodwad SM, Savage J, Scharschmidt TJ, Patel A. Evaluation and treatment of spinal metastatic disease. Cancer Treat Res. 2014 Jul 29;162:131-50.

4. Brown MD, Gomez-Marin O, Brookfield KF, Li PS. Differential diagnosis of hip disease versus spine disease. Clin Orthop Relat Res. 2004 Feb;419:280-4.

5. Plastaras CT. Electrodiagnostic challenges in the evaluation of lumbar spinal stenosis. Phys Med Rehabil Clin N Am. 2003 Feb;14(1):57-69.

6. Rainville J, Lopez E. Comparison of radicular symptoms caused by lumbar disc herniation and lumbar spinal stenosis in the elderly. Spine (Phila Pa 1976). 2013 Jul 1;38(15):1282-7.

7. Genevay S, Atlas SJ. Lumbar spinal stenosis. Best Pract Res Clin Rheumatol. 2010 Apr;24(2):253-65.

8. Binder DK, Schmidt MH, Weinstein PR. Lumbar spinal stenosis. Semin Neurol. 2002 Jun;22(2):157-66.

9. Lurie J, Tomkins-Lane C. Management of lumbar spinal stenosis. BMJ. 2016 Jan 4;352:h6234.


Monday, December 27, 2021

Lower Spine and Lower Extremity Physical Examination

Written by Travis Brege with Dr. Nabil Ebraheim

The steps of any orthopedic examination will follow the pattern of inspection, palpation, range of motion, and tests of strength for the key groups of muscles applying all the appropriate provocative tests and neurovascular examinations. 

First, in the inspection of the spine, look for any visible deformities in the coronal (frontal) and sagittal (longitudinal) planes. In the coronal plane, check for scoliosis and pelvic obliquity1. In the sagittal plane, check for normal cervical lordosis, thoracic kyphosis, and lumbar lordosis2. While assessing the symmetry of the whole body, make sure to assess the skin for lesions, hairy patches, dimples, surgical scars, muscular atrophy, and anything else that may be abnormal.

Next, you want to palpate the iliac crests, posterior superior iliac spines, spinous processes, sacrum, trochanters, and ischial tuberosities. Palpate the soft tissue as well, assessing trigger points such as the gluteus muscles, piriformis, and sciatic nerve. 

Assess the patient’s movement first with their gait as certain gaits may indicate various pathologies (ie. antalgic, Trendelenburg, steppage, and staggering gaits)3. Then, check the movements of the lower spine to identify if any causes pain; for example, extension of the spine creates pain in lumbar stenosis4, while spinal flexion can create pain when a disk pathology is present5.

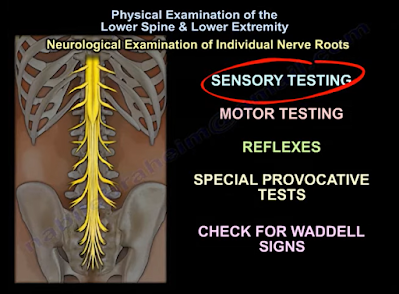
Now, we can assess the individual nerve roots from L2-S1 using sensory and motor testing, reflex tests, specific provocative tests, and check for Waddell Signs. 

In sensory testing, the areas that can be assessed include pain, light touch, temperature, and proprioception (awareness of the position of one’s body). Sensory testing can indicate a spinal root pathology in the presence of a dermatomal pattern of dysfunction, or it can suggest a neuropathy in the presence of a glove-and-stocking distribution of sensory dysfunction6. The specific pattern of sensory distribution in the lower extremities can be normal, impaired, or completely absent in some cases. 

In motor testing, the action of hip flexion comes largely from the iliopsoas muscle, which is innervated by the L1, L2, and L3 lumbar nerve roots. Hip abduction is completed through the L2, L3, and L4 lumbar nerve roots. Knee extension is innervated by the L2, L3, and L4 lumbar nerve roots. Dorsiflexion is largely performed via the tibialis anterior muscle which is innervated by the L4 lumbar nerve root. Extension of the hallux is mainly innervated by the L5 lumbar nerve root. Ankle plantarflexion is performed using the gastro-soleus complex whose main innervation is from the S1 sacral nerve root7. 

For reflexes, only two exist in the lower extremity that are utilized in physical examination. The Patellar Reflex which is innervated by the L4 lumbar nerve root, and the Achilles Tendon Reflex which is innervated by the S1 sacral nerve root7. 

Provocative and special tests can be used to help differentiate between musculoskeletal pathology and spinal pathology. These include the Straight Leg Raising Test for L5-S1 nerve root irritation8 and the Femoral Stretch Test for L3-L4 nerve root irritation9. Upper motor neuron lesions can be identified or ruled out utilizing the Clonus Test10 and the Babinski Test11. The Bulbocavernosus Reflex can be utilized to detect spinal shock12. The Faber (Flexion, ABduction, External Rotation) Test is a good test for assessing the sacroiliac joint, but it is NOT confirmatory13,14. Sacroiliac joint test is usually confirmed by the injection of an anesthetic with a positive response for reduction of pain15.

Waddell’s Signs are controversial, however, assessing for these signs can be included as a part of a thorough physical examination for a patient that presents with lower back pain. Waddell’s Signs include: (1) superficial tenderness, (2) non-anatomical tenderness (tenderness that exists over a wide area that goes beyond a single anatomical boundary), (3) axial loading pain on the patient’s head that elicits low back pain, (4) acetabular rotation causing low back pain, (5) distracted straight leg discrepancy, (6) regional sensory disturbances, (7) regional muscle weakness that can’t be explained on an anatomical basis, and (8) overreaction to a pain stimulus that isn’t reproduced when the same provocation is applied at a later time16.


References

1. Janicki JA, Alman B. Scoliosis: Review of diagnosis and treatment. Paediatr Child Health. 2007 Nov;12(9):771-6. doi: 10.1093/pch/12.9.771. PMID: 19030463; PMCID: PMC2532872. 

2. Scheer JK, Tang JA, Smith JS, Acosta FL Jr, Protopsaltis TS, Blondel B, Bess S, Shaffrey CI, Deviren V, Lafage V, Schwab F, Ames CP; International Spine Study Group. Cervical spine alignment, sagittal deformity, and clinical implications: a review. J Neurosurg Spine. 2013 Aug;19(2):141-59. doi: 10.3171/2013.4.SPINE12838. Epub 2013 Jun 14. PMID: 23768023. 

3. Lim MR, Huang RC, Wu A, Girardi FP, Cammisa FP Jr. Evaluation of the elderly patient with an abnormal gait. J Am Acad Orthop Surg. 2007 Feb;15(2):107-17. doi: 10.5435/00124635-200702000-00005. PMID: 17277257.

4. Katz JN, Harris MB. Clinical practice. Lumbar spinal stenosis. N Engl J Med. 2008 Feb 21;358(8):818-25. doi: 10.1056/NEJMcp0708097. PMID: 18287604.

5. Kuai S, Liu W, Ji R, Zhou W. The Effect of Lumbar Disc Herniation on Spine Loading Characteristics during Trunk Flexion and Two Types of Picking Up Activities. J Healthc Eng. 2017;2017:6294503. doi: 10.1155/2017/6294503. Epub 2017 Jun 11. PMID: 29065628; PMCID: PMC5485332.

6. Scott K, Kothari MJ. Evaluating the patient with peripheral nervous system complaints. J Am Osteopath Assoc. 2005 Feb;105(2):71-83. doi: 10.7556/jaoa.2005.105.2.71. PMID: 15784929.

7. Basit H. Anatomy, Back, Spinal Nerve-Muscle Innervation [Internet]. StatPearls [Internet]. U.S. National Library of Medicine; 2021 [cited 2021Oct25]. Available from: https://www.ncbi.nlm.nih.gov/books/NBK538322/?report=classic

8. Capra F, Vanti C, Donati R, Tombetti S, O'Reilly C, Pillastrini P. Validity of the straight-leg raise test for patients with sciatic pain with or without lumbar pain using magnetic resonance imaging results as a reference standard. J Manipulative Physiol Ther. 2011 May;34(4):231-8. doi: 10.1016/j.jmpt.2011.04.010. Epub 2011 May 5. PMID: 21621724.

9. Suri P, Rainville J, Katz JN, Jouve C, Hartigan C, Limke J, Pena E, Li L, Swaim B, Hunter DJ. The accuracy of the physical examination for the diagnosis of midlumbar and low lumbar nerve root impingement. Spine (Phila Pa 1976). 2011 Jan 1;36(1):63-73. doi: 10.1097/BRS.0b013e3181c953cc. PMID: 20543768; PMCID: PMC2978791.

10. Zimmerman B, Hubbard JB. Clonus. 2021 Aug 12. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2021 Jan–. PMID: 30521283.

11. van Gijn J. The Babinski reflex. Postgrad Med J. 1995 Nov;71(841):645-8. doi: 10.1136/pgmj.71.841.645. PMID: 7494766; PMCID: PMC2398330.

12. Ko HY. Revisit Spinal Shock: Pattern of Reflex Evolution during Spinal Shock. Korean J Neurotrauma. 2018 Oct;14(2):47-54. doi: 10.13004/kjnt.2018.14.2.47. Epub 2018 Oct 31. PMID: 30402418; PMCID: PMC6218357.

13. Cattley P, Winyard J, Trevaskis J, Eaton S. Validity and reliability of clinical tests for the sacroiliac joint. A review of literature. Australas Chiropr Osteopathy. 2002 Nov;10(2):73-80. PMID: 17987177; PMCID: PMC2051080.

14. Nejati P, Sartaj E, Imani F, Moeineddin R, Nejati L, Safavi M. Accuracy of the Diagnostic Tests of Sacroiliac Joint Dysfunction. J Chiropr Med. 2020 Mar;19(1):28-37. doi: 10.1016/j.jcm.2019.12.002. Epub 2020 Sep 12. PMID: 33192189; PMCID: PMC7646135.

15. Jung MW, Schellhas K, Johnson B. Use of Diagnostic Injections to Evaluate Sacroiliac Joint Pain. Int J Spine Surg. 2020 Feb 10;14(Suppl 1):30-34. doi: 10.14444/6081. PMID: 32123655; PMCID: PMC7041665.


Monday, December 20, 2021

Neck and Upper Extremities Examination

 Written by Ryan Jones with Dr. Nabil Ebraheim

Neck and upper extremities spine examination or cervical spine physical examination involves assessment of vertebrae C3-T2, cranial nerve roots C4-T1, and all the muscles innervated by these nerve roots along with the muscles associated with basic neck movement. This examination follows the typical pattern of orthopedic examination of inspection, palpation, range of motion, neurological evaluation, and special tests1.

Inspection

Check for any visual deformities or abnormal anatomical alignments in the coronal and sagittal plane including typical cervical lordosis and thoracic kyphosis1. Also, look for any surgical scars, skin defects like café au lait spots, or muscular atrophy2. Muscular atrophy can present as shoulder imbalance, scapular winging, or a general unilateral reduction in size of muscles of the upper extremities.

Palpation

Palpate for local tenderness along the spinal axis while also looking for any asymmetry2. This includes palpations of the spinous processes and facet joints of the vertebrae along with palpation of the scapula to look for any asymmetry. Palpate the paraspinal muscles while looking for any tenderness or asymmetry. The muscles of importance include the trapezius, rhomboids, and levator scapulae muscles1,3.

Range of Motion

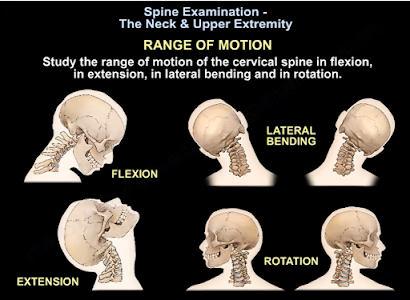
Range of motion for the cervical spine involves checking cervical flexion (normal = 50), extension (normal = 60), rotation (normal = 80), and lateral bending (normal = 45)2. A thorough range of motion examination should also be done for the shoulder due to the extensive nerve root innervation. Shoulder range of motion involves testing abduction (normal = 180), adduction (normal = 45), flexion (normal = 90), extension (normal = 45), internal rotation (normal = 55), and external rotation (normal = 45)4. Any abnormalities in range of motion can be indicative of muscular or neurological pathologies.

Neurological Examination

Test the motor ability and strength of the muscles associated with each cranial root for strength by grading it 0-V based on the muscle manual testing grading system2,3. Any weakness is a sign of muscular or neurological pathology. Next, test for sensory function for pain (with a paper clip) and light touch (finger) sensation at the dermatome for each cranial nerve1. Any abnormalities may be a result of neurological pathologies. Test the biceps reflex for C5, brachioradialis reflex for C6, and triceps reflex for C7 cranial nerve root abnormalities1.

Special Tests

Use the following provocative test to differentiate neck pathologies from other upper extremity:

·         Spurling’s test is indictive of acute radioculopathy2.

·         Hoffman’s test is indictive of cervical myelopathy2.

·         Lhermitte’s test is indicative of compression and myelopathy of the cervical spine2.

·         Stretch test is indicative of brachial plexus pathology.

·         Compression test is indicative of narrowing of the neural foramen, facet joint pressure, or muscle spasms from the paraspinal muscles3.

·         Observation of steppage, lateral, or wide-base gait are all indicative of myelopathy or neurological pathology2.

Remember that an MRI may be required to confidently differentiate between shoulder and neck pathologies1.

References

1.       Ebraheim N. Spine Exam & Upper Extremity – Everything You Need to Know – Dr. Nabil Ebraheim [Internet]. Toledo (OH): University of Toledo Medical Center, Department of Orthopedics; 2021 Aug 4 [cited 2021 Oct 23]. Available from: https://www.youtube.com/watch?v=hIiV-xi2TiE.

2.       Moore DW. Neck & Upper Extremity Spine Exam [Internet]. Santa Barbara (CA): Santa Barbara Orthopedic Associates; 2021 June 27 [cited 2021 Oct 23]. Available from: https://www.orthobullets.com/spine/2001/neck-and-upper-extremity-spine-exam

3.       Iyer KM. Examination of the Cervical Spine. In: Clinical Examination in Orthopedics. London: Springer; 2012. pp 97-107.

4.       Iyer KM. Examination of the Shoulder. In: Clinical Examination in Orthopedics. London: Springer; 2012. pp 9-18.


Neck Pain Causes and Treatment -Everything You Need to Know

Written by Katherine Esser and Dr. Nabil Ebraheim

Neck pain is a common ailment of the American population, affecting 30 to 50% of adults annually1. While there are numerous etiologies of neck pain, this is a brief review of the more common causes and modes of treatment2.


Firstly, radiculopathy from disc herniation. In addition to neck pain, the patient will complain of arm pain that typically follows a myotomal pattern, and sensory symptoms (like burning and tingling) that follow a specific dermatome in the hand3. There may also be motor weakness of the upper extremity3. This is due to compression of a nerve root either by a disc herniation or by arthritis that narrows the foramen2. A neurological exam assessing motor, sensory and reflex testing should be done to determine cervical spine disc herniation. Treatment should first be non-surgical with anti-inflammatory medication, isometric exercises, physical therapy, and muscle relaxants2. An MRI should be ordered if symptoms do not improve after 6-12 weeks of conservative treatment. If there is an indication for surgery, it often involves decompression and fusion of the involved disc space. 26% of patients with cervical radiculopathy require surgery3.

Secondly, neck pain may be due to cervical myelopathy. This is the most common cause of non-traumatic spinal cord dysfunction4. It is due to direct compression of the spinal cord or surrounding blood vessels, and presents in a variety of ways clinically4. Indications of cervical myelopathy are an unstable and wide-based gait, clumsiness of the hands, occipital headaches, and discomfort of the neck2. The pain may not be severe, but insidious, gradual, and poorly characterized. An MRI may be ordered which will show compression of the spine2. Due to the slow, stepwise deterioration in cervical myelopathy, each stage may be treated differently4. There is conflicting evidence regarding the conservative versus surgical approach to treatment of cervical myelopathy. The goal for surgery is cord decompression with expansion of the spinal canal, restoration of cervical lordosis, and stabilisation if the risk of cervical kyphosis is high4. The evidence suggests mild cervical myelopathy should be treated conservatively with careful observation, whereas surgical intervention should be employed for moderate to severe cases4.

Thirdly, neck pain may be due to a whiplash injury. This is the most common traumatic cause of neck pain5. Specifically, neck hyperreflexia and neck pain after a car collision from behind. Pain may refer to the head, shoulder, or arm. There are usually no neurological deficits. The patient will have a soft tissue injury and an x-ray will show cervical lordosis due to muscle spasm. Treatment for a whiplash injury is aggressive physical therapy and mobilization.

Cervical spondylosis may also cause neck pain. This is arthritis of the spine. It is a natural degenerative process of cervical spine which will be shown on X-Ray. Degenerative changes start in the intervertebral discs with osteophyte formation and involvement of soft tissue structures. It is important to note many people over 30 years of age display similar abnormalities on imaging of the cervical spine and it may be difficult to delineate normal aging and disease. Cervical spondylosis can be diagnosed clinically based on characteristic exacerbation by neck movement. Although pain is focused in the cervical area, it is also referred to a wide area6. Cervical spondylosis should be managed medically and surgery should only be done if there is instability or neurological deficit3. In fact, there is evidence that suggests various exercise regiments may be more effective than usual medicinal care (analgesics, muscle relaxants) or stress management6.

While there are various pathologies to include in the differential of neck pain, typically, patients with neck pain will have no injury. Pain will be in the posterior neck, tender to palpation with no radiation to the arm, no neurological deficits, and an X-Ray will show mild arthritis. Often, patients will be prescribed anti-inflammatory medication and referred to physical therapy.


References

1.       Goode AP, Freburger J, Carey T. Prevalence, practice patterns, and evidence for chronic neck pain. Arthritis Care Res (Hoboken). 2010 Nov;62(11):1594-601. doi: 10.1002/acr.20270. Epub 2010 Jun 2. PMID: 20521306; PMCID: PMC2974793.

          Ebraheim N. Neck pain causes and treatment - everything you need to know - Dr. Nabil Ebraheim [Internet]. YouTube. YouTube; 2021 [cited 2021Nov24]. Available from: https://www.youtube.com/watch?v=bwM5uskViJ4&ab_channel=nabilebraheim

3.       Wong JJ, Côté P, Quesnele JJ, Stern PJ, Mior SA. The course and prognostic factors of symptomatic cervical disc herniation with radiculopathy: a systematic review of the literature. Spine J. 2014; 14(8):1781-9.

4.       Bakhsheshian J, Mehta VA, Liu JC. Current Diagnosis and Management of Cervical Spondylotic Myelopathy. Global Spine J. 2017 Sep;7(6):572-586. doi: 10.1177/2192568217699208. Epub 2017 May 31. PMID: 28894688; PMCID: PMC5582708.

5.       MacDermid JC, Walton DM, Bobos P, Lomotan M, Carlesso L. A Qualitative Description of Chronic Neck Pain has Implications for Outcome Assessment and Classification. Open Orthop J. 2016 Dec 30;10:746-756. doi: 10.2174/1874325001610010746. PMID: 28217199; PMCID: PMC5301418.

6.       Binder AI. Cervical spondylosis and neck pain. BMJ. 2007 Mar 10;334(7592):527-31. doi: 10.1136/bmj.39127.608299.80. PMID: 17347239; PMCID: PMC1819511.


Monday, December 13, 2021

ACL Ganglion Cyst, Meniscal Cyst, Baker Cyst - Everything You Need to Know

ACL Ganglion Cyst, Meniscal Cyst, Baker Cyst - Everything You Need to Know

Written by Ali Mahmoud with Dr. Nabil Ebraheim

 There are many cysts that can occur in and around the knee joint. These types of cysts include an anterior cruciate ligament (ACL) ganglion cyst, meniscal cyst, and baker’s cyst.

Ganglion cysts contain yellow viscous fluid surrounded by a thin capsule, and are considered rare when associated with the ACL (1). Theorized pathogenesis of an ACL ganglion cyst includes synovial tissue herniation, post-traumatic mucoid degeneration mediated by local release of hyaluronic acid, ectopic synovial tissue theory, and displacement of synovial fluid during embryogenesis. These cysts are often discovered during knee MRI or knee arthroscopy while evaluating symptoms of knee pain or limited knee motion. There are no defining symptoms of ACL ganglion cysts, but they should be suspected in patients with knee pain or limited range of motion in their knees. MRI’s are the gold standard for diagnosing ACL ganglion cysts, with the diagnostic criteria being a fluid signal in the substance of the ligament with two of the following three criteria: 1) mass effect on ACL fibers, 2) lobulated margins, and 3) ACL fluid disproportionate to the joint. The treatment of choice for an ACL ganglion cyst is an arthroscopic decompression with debridement of the cyst for instant relief of pain, range of motion improvement, and return to physical activities. In cases where arthroscopic decompression is not available, aspiration under CT or ultrasound have shown excellent results in treating these cysts. These cysts do not recur after resection (2).

Meniscal cysts are believed to occur when the meniscal fibrocartilage tears, allowing synovial fluid to extrude through the meniscal tear and become encysted. Meniscal cysts can be classified into 3 subtypes: parameniscal, intrameniscal, and synovial. Parameniscal cysts appear on MRI as a loculated fluid-intensity lesion with a clear connection to the adjacent meniscus (4). Intrameniscal cysts appear as an abnormally increasing signal within an enlarged meniscus. Synovial meniscal cysts are cystic outpouchings of the joint capsule that are not associated with trauma. They are frequently asymptomatic, and are found incidentally on MRIs performed to assess for other knee pathologies. Symptomatic meniscal cysts can be treated with arthroscopic resection and repair of the causative meniscal tear (3).

Baker’s cyst (popliteal cyst) is the most common cyst in the knee (3). These are fluid-filled lesions arising in the popliteal fossa as an enlargement of the gastrocnemio-semimembranosus bursa. These cysts can expand into the spaces between muscle and knee capsule. Rarely, they can extend into nearby muscles such as the vastus medialis muscle and the head of the gastrocnemius muscle (6). Complications of a Baker’s cyst include rupture, hemorrhage and infection. Most Baker’s cysts are asymptomatic, but larger ones may cause nerve entrapment, compress nearby veins, or limit knee range of motion (3). Cysts that rupture can cause symptoms similar to phlebitis (5). They can be visualized on MRI along with any associated pathology that is causing the cyst, such as arthritis or meniscal tear. They can be treated conservatively with rest, ice, and anti-inflammatory medications. They can also be treated with aspirations, steroid injections or surgical excisions. If an intra-articular pathology is present that is causing the cyst, then treatment with arthroscopy and debridement of the pathology is recommended to prevent recurrence of the Baker’s cyst.


Citations

1.       Plotkin B, Agarwal VK, Varma R. Ganglion Cyst of the Anterior Cruciate Ligament. Radiology Case Reports. 2009;4(3):1-4.

2.       Vaishya R, Esin Issa A, Agarwal AK, Vijay V. Anterior Cruciate Ligament Ganglion Cyst and Mucoid Degeneration: A Review. Cureus. 2017 Sep 13;9(9):e1682. doi: 10.7759/cureus.1682. PMID: 29152439; PMCID: PMC5679775.

3.       Telischak NA, Wu JS, Eisenberg RL. Cysts and cystic-appearing lesions of the knee: A pictorial essay. Indian J Radiol Imaging. 2014 Apr;24(2):182-91. doi: 10.4103/0971-3026.134413. PMID: 25024531; PMCID: PMC4094974.

4.       Crowell MS, Westrick RB, Fogarty BT. Cysts of the lateral meniscus. Int J Sports Phys Ther. 2013 Jun;8(3):340-8. PMID: 23772349; PMCID: PMC3679639.

5.       Handy JR. Popliteal cysts in adults: a review. Semin Arthritis Rheum. 2001 Oct;31(2):108-18. doi: 10.1053/sarh.2001.27659. PMID: 11590580.

6.       Li TY. The Sonographic Spectrum of Baker Cysts. Journal of Diagnostic Medical Sonography. 2017 Sep 9;34(1):38-48. doi: 10.1177/8756479317733750. 

Monday, December 6, 2021

What is Bursitis? - Everything You Need to Know

 What is Bursitis?

Written by Braden Womack with Dr. Nabil Ebraheim

Bursas are synovium-lined, sac-like structures located throughout the body between skin and tendon or tendon and bone (1,2). The main function of bursa is to reduce the friction between areas of movement and some common locations are the shoulder, knee, hip, and elbow (1). When these areas become swollen or inflamed it is known as bursitis. During this abnormality the bursa will enlarge with fluid causing any movement against or direct pressure upon the area to produce pain for the patient (2).

There are many causes of bursitis that one should be aware of, five of which are prolonged pressure, trauma, sepsis, autoimmune conditions, and idiopathic origins. Prolonged pressure is when the bursa is stressed between a hard surface and bony prominence. Examples of this prolonged pressure include over-use of the area with repetitive motions, frequently resting one’s elbow on their desk, and working on one’s knees without adequate padding. Traumatic bursitis is caused when direct pressure is applied to the bursa, often unknowingly as it may have seemed benign at the time (2). Traumatic bursitis does put the patient at risk of developing septic bursitis, often difficult to distinguish against aseptic bursitis, which is most induced by invasive procedures (2,3). Staphylococcus aureus causes roughly 80% of septic bursitis through what is believed to be a direct inoculation, instead of a hematogenous route due to the poor blood flow seen to bursas (4). Bursitis can also be caused by autoimmune conditions such as rheumatoid arthritis, osteoarthritis, systemic lupus erythematosus, scleroderma, spondyloarthropathy, and gout. The last common cause of bursitis is idiopathic in origin (2).


Bursitis can be broken up further to acute bursitis and chronic bursitis. Acute bursitis is typically caused by trauma, infection, or crystalline joint disease resulting in pain on palpation of the bursa as well as a decrease in range of motion that is secondary to pain. Whereas chronic bursitis is typically caused by inflammatory arthropathies, repetitive motions, or microtraumas most often causing painless swelling and thickening of the bursa. Examination of the skin is an important distinguishing factor for acute and chronic bursitis as trauma, erythema, and warmth should all be evaluated to make a proper diagnosis (2).


Diagnosis of many types of bursitis can be made clinically without further studies, however in the case of trauma, concern for foreign bodies, or fractures imaging can play an important role in diagnosis. Basic plain film imaging can be used when evaluating a superficial bursa however, for a deeper bursa MRI and ultrasound can be used (1). Ultrasound will also provide the added benefit of showing real-time images to observe changes in active and passive movements (2). When evaluating an inflamed bursa, aspiration is a critical tool to distinguish between septic and aseptic bursitis as the aspirated fluid should be sent for a basic cell count and cell cultures (3).

Treatment for bursitis depends on the type and causative agent as most bursitis will heal on their own without intervention. To combat the patient’s pain, bursitis can be treated with a conservative treatment plan involving rest, ice, compression, and elevation as well as NSAIDS and/or acetaminophen for pain (2). With deeper bursitis corticosteroid injections can provide symptomatic relief however, this course of treatment is not recommended for superficial bursa and can delay the diagnosis of another condition such as a tear. Physical therapy is another important treatment method to strengthen the muscles that support the area around the bursa (2). For septic bursitis the typical course of treatment is oral antibiotics as an outpatient but systemic IV antibiotics may be needed if signs of widespread sepsis are present (4). The last line of treatment is surgery which is most often used only as a last resort when all other conservative treatment methods fail (2).


References
1. Chatra PS. Bursae around the knee joints. Indian J Radiol Imaging. 2012 Jan;22(1):27-30. doi: 10.4103/0971-3026.95400. PMID: 22623812; PMCID: PMC3354353.

2. Williams CH, Jamal Z, Sternard BT. Bursitis. [Updated 2021 Aug 2]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2021 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK513340/ 

3. Aaron, Daniel L. MD; Patel, Amar MD; Kayiaros, Stephen MD; Calfee, Ryan MD Four Common Types of Bursitis: Diagnosis and Management, American Academy of Orthopaedic Surgeon: June 2011 - Volume 19 - Issue 6 - p 359-367

4. Cea-Pereiro JC, Garcia-Meijide J, Mera-Varela A, Gomez-Reino JJ. A comparison between septic bursitis caused by Staphylococcus aureus and those caused by other organisms. Clin Rheumatol. 2001;20(1):10-4. doi: 10.1007/s100670170096. PMID: 11254233.


Monday, November 29, 2021

Hypermobile Ehlers-Danlos Syndrome (hEDS)

Hypermobile Ehlers-Danlos Syndrome

Written by Sarit Dhar with Dr. Nabil Ebraheim

While some people know what Ehlers-Danlos Syndrome (EDS) is, not many know that it is actually a group of 13 different disorders or types. One of the most prevalent types is Hypermobile Ehlers-Danlos Syndrome (hEDS), accounting for 80-90% of EDS cases [1]. The Ehlers-Danlos Syndromes are defined as inherited connective tissue disorders, affecting structural proteins (namely collagen) that leads to joint hypermobility, skin hyperextensibility, and tissue fragility [2]. hEDS is the only EDS subtype that does not have a currently known genetic basis, though it is a hereditary disorder with autosomal dominant inheritance pattern [2]. Therefore, hEDS is in part a diagnosis of exclusion, as genetic testing can be done for the other subtypes. 

The Ehlers-Danlos Syndromes as whole are related to the Joint Hypermobility Spectrum, a spectrum of disorders intended to classify different severities of Hypermobility Spectrum Disorders (HSD). At the most extreme end of the hypermobile spectrum lies hEDS [3]. hEDS differs from the other EDS subtypes in its presentation as well. hEDS includes general joint hypermobility (GJH) but has less severe skin involvement compared to classical or vascular EDS types [1]. Easy bruising and impaired wound healing are also common. The definition of hEDS has evolved to include chronic pain and chronic fatigue as common presentations in those affected by the disease. The current diagnostic criteria include confirmation of GJH using the Beighton scoring system, positive musculoskeletal and pain symptoms or family history, and exclusion of other EDS subtypes or HSDs [4]. 

(Visit this link for the full diagnostic criteria of hEDS)

Apart from acute complications such as dislocation and subluxation, hEDs treatment revolves around chronic pain management and prevention of complications [1]. Acute exacerbations should be treated accordingly using joint reduction techniques and acute pain management. Physical therapy can be used to increase joint stability using low resistance exercises and stretching to increase muscle tone, thereby reducing the chance of acute joint injury. Patients should generally avoid hyperextension and high impact exercise. Oral acetaminophen, NSAIDs, and COX-2 inhibitors can be used as analgesics for chronic pain, as well as after acute injury. Cannabinoids can be considered for chronic pain, but opiates should rarely be used. If an hEDS patient must undergo surgery, careful technique should be used to minimize the wound site and promote healing. In summary, it is important to understand hEDS and how it differs from EDS and other HSDs to properly diagnose and treat patients.


References

1. Tinkle B, Castori M, Berglund B, Cohen H, Grahame R, Kazkaz H, et al. Hypermobile Ehlers-Danlos syndrome (a.k.a. Ehlers-Danlos syndrome Type III and Ehlers-Danlos syndrome hypermobility type): Clinical description and natural history. American Journal of Medical Genetics Part C: Seminars in Medical Genetics. 2017 Feb 1;175(1):48–69.

2. The Types of EDS [Internet]. The Ehlers Danlos Society. 2017. Available from: https://www.ehlers-danlos.com/eds-types/

3. What are the hypermobility spectrum disorders? [Internet]. The Ehlers Danlos Society. 2017. Available from: https://www.ehlers-danlos.com/what-is-hsd/

4. Forghani I. Updates in Clinical and Genetics Aspects of Hypermobile Ehlers Danlos Syndrome. Balkan Medical Journal. 2019 Jan 10;36(1):12–6.