Showing posts with label Medical School. Show all posts

Tuesday, October 30, 2018

Olecranon Fractures


Fractures of the olecranon may occur due to a direct blow to the elbow or from a fall onto an outstretched hand. Nondisplaced fractures have less than 2mm of separation and are considered stable. Fracture separation will not increase with elbow flexion. Extensor mechanism is intact and the patient will be able to extend the elbow against gravity. Displaced fractures could be an avulsion, oblique, transverse, comminuted, or dislocated.
Olecranon fracture dislocations can be anterior (transolecranon) or posterior (similar to monteggia fracture dislocation). An examination will show that the patient is unable to extend the elbow with these displaced fracture types. A true lateral view x-ray will clearly show the olecranon fracture. Usually, these fractures are followed by stiffness of the elbow in about 50% of the patients. However, this does not affect the function.
The goal of treatment for olecranon fractures should be restoration of the articular surface, preservation of the continuity of extensor mechanisms, maintain elbow stability, and avoid stiffness of the elbow. Nonoperative treatment is used for nondisplaced fractures and it may be used for some displaced fractures in elderly patients (treat elbow in some flexion with a splint). I would personally use minimally invasive techniques in these patients unless the skin is very bad, or the fracture is very comminuted.
There are three techniques used for surgical treatment: the tension band technique, detach olecranon and reattach triceps, and plate and screw fixation. The tension band technique is only used for transverse fractures with no comminution. K-wires and screws are used, and the surgeon may use either a 6.5mm screw or Kwires for the tension band. When doing the tension band technique, you want to engage the anterior cortex of the ulna. The surgeon should avoid over penetration to avoid affecting the forearm rotation or injuring the anterior interosseous nerve. The surgeon needs to be sure that the pins are not fixing the radius and that after the operation, the patient can perform pronation and supination of the forearm (pull the pins out slightly if needed). The distractive force of the triceps is converted to compression force at the articular surgace, especially when bending the elbow. The drill hole for the K-wire should be positioned about 4-5cm from the fracture which gives enough safe distance so that the fracture will not propagate. Place the tension band wire through the drilled holes before application of the K wires. The surgeon should be sure that the hook to the K-wire is posterior. Make sure that the tension band wire is close to the bone so there is no laxity in the fixation and instability. An intramedullary screw could be used. This screw fixation may need a washer to capture the tension band wire. Intramedullary 6.5mm screw fixation is a reasonable option for fixation but it may need to be supplemented with tension band wires. Never use cancellous screw alone. The tension band technique are for transverse fractures of the olecranon. If fractures comminution is present, change the plan of fixation.

When detaching the olecranon and reattaching the triceps, an excision of the fracture fragment and triceps advancement is used:

  • If the fracture is less than 50%
  • To treat elderly patients (especially if fracture is comminuted)
  • For some nonunions when the fracture is small and cannot be fixed

The surgeon must be sure that the procedure is done with the elbow is stable. If the elbow has ligamentous instability and excision of the fracture fragment is done, this will make the elbow very unstable. The triceps should be attached closer to the articular surface.
Special olecranon plates are available when using a plate and screw fixation technique. The bridge plate and screw fixation technique is used in comminuted, Monteggia, oblique fractures extending to the coranoid, and fracture dislocation. The plate is placed on the tension side of the olecranon (dorsal side). Sometimes, an opening is made through the triceps and the plate is placed against the bone, then suturing the triceps tendon over the plate to avoid hardware prominence.
In summary, if the patient is elderly with a small, comminuted fracture fragment less than 50% of the joint space, excise the fragment, and reattach the triceps tendon to the olecranon. If the olecranon fracture is transverse and proximal to the base of the coranoid process, then use the tension band technique. Use plate fixation for all olecranon fracture scenerios, such comminuted fractures, oblique fractures, unstable fractures, dislocation, or fractures distal to the coranoid process. The typical exam question scenario will discuss a comminuted fracture that should be treated with a plate. You probably need to remove above 20% of the plate fixations due to hardware irritation. Hardware irritation is worse with the tension band surgical treatment (may need to remove in more than 50% of cases).

Tuesday, October 9, 2018

Anterior Interosseous Nerve- The Benedictine and O.K. Sign


A patient with a complete anterior interosseous nerve injury or a high medial nerve injury should be asked to make a fist. The first and second digits will have difficulty in flexing, while the other digits will flex. The third digit will be weak, while the fourth and fifth digits are normal. This position of the hand is similar to the position taken during a hand blessing. The Benedictine sign is different from an “ulnar claw hand”. Ulnar claw hand refers to damage to the ULNAR nerve and is seen when attempting to extend all the digits (leaving the 4th and 5th digits flexed). The O.K. sign is used to check for paralysis of the anterior interosseous nerve due to entrapment or compression injury. A patient with paralysis of the anterior interosseous nerve will be unable to make the O.K. sign. This is due to weakness of the flexor pollicis longus and flexor digitorum profundus muscles. A typical pinch attitude is associated with anterior interosseous nerve injury.

The anterior interosseous nerve arises from the median nerve about 4-6cm distal to the elbow, which is about 1/3 of the way down the forearm. It exits from the anterolateral aspect of the median nerve and it runs between the radius and the ulna on the interosseous membrane between and below the muscles of the flexor digitorum profundus and the flexor pollicis longus.
The anterior interosseous nerve supplies the flexor digitorum profundus muscle for the index and long fingers. It also supplies the flexor pollicis longus and the pronator quadratus muscles. The flexor digitorum profundus muscle for the index and long fingers is supplied by the anterior interosseous nerve. The medial part of the FDP is supplied by the ulnar nerve (FDP has dual innervation). The anterior interosseous nerve passes dorsal to the pronator quadratus with the anterior interosseous artery and provides innervation to the volar wrist capsule. The terminal branch of the anterior interosseous nerve innervates the carpal joint capsule.


In patients with Martin-Gruber Connection, the median nerve, or anterior interosseous nerve to the ulnar nerve in the forearm may present with intrinsic muscle weakness. It may be differentiated also from Parsonage-Turner Synrome (acute brachial plexus neuritis) and patient may have pain in the affected extremity. In anterior interosseous nerve entrapment, the median nerve conduction study result will be normal, however the needle EMG of the anterior interosseous innervated muscles will be abnormal.

Tuesday, October 2, 2018

Tests Orthopaedic Surgeons Should Think About


There are some important tests that every Orthopaedic Surgeon should think about. This doesn’t mean the tests are needed for every patient. It just means that the physician needs to think about these tests to see if it will benefit the patient or not. Some tests commonly ordered are hemoglobin A1C (HbA1c), Vitamin D25, and C-reactive protein (CRP) & sedimentation rate.


Hemoglobin A1C test are ordered for diabetic patients. HbA1c is a good test for monitoring long-term glucose (sugar) control on patients with diabetes. HbA1c is a percentage of the glycanated hemoglobin relative to the total hemoglobin in the blood. The normal range of HbA1c is 4-6%. More than 7% is high. Another test, the 25-Hydroxy Vitamin D blood test is ordered for patients with osteoporosis, nonunions, fragility fractures, and occasionally in patients with infections. If infection is suspected and the physician needs to monitor the progress of treatment, C-reactive protein (CRP) & sedimentation rate tests should be ordered. A Methicillin-resistant staphylococcus aureus (MRSA) screening should be ordered for patients who could be carriers. Nutritional assessments may be necessary for other patients.

Joints should be aspirated prior to injecting of the joint. The physician should additionally be sure that there is no infection when injecting the joint. A fluid analysis from the joint should be completed. Important vascular studies that can be ordered include: A.B.I., CTA, or a Doppler. Some radiological studies are performed with a dye injection. For example, an MRI of the spine will require gadolinium, while an MRI arthrogram may be used for the hip or shoulder. Tests rarely ordered include: alpha-defensin test (infection); Nicotine/Cotinine test (smoking); Protein S, Protein C, or Factor 5 leiden tests. There are some special tests and precautions that must be taken for patients with epilepsy. It is important that the physician does not perform a procedure if the epilepsy is not controlled. It is important to know that anti-epileptic medication can interfere with vitamin D metabolism in the liver.
Patients on anticoagulation medications should be monitored, especially patients with atrial fibrillation, which makes the orthopaedic procedure more complicated. You want to give the patient anticoagulation, but not encroaching on the management of atrial fibrillation. Patients with a short or thick neck, or a history of sleep apnea, may need additional sleep studies before surgery and may need special precautions after surgery. Sleep apnea will affect the post-operative care of the patient. The physician should avoid ordering unnecessary tests and focus on ordering the most important tests. Orthopaedics deal with concepts and every condition will have a reasonable way of diagnosing it and a reasonable way of treating it.  

Wednesday, September 26, 2018

Adhesive Capsulitis, Frozen Shoulder


Adhesive Capsulitis, or frozen shoulder, is a painful progressive loss of shoulder motion. It affects both active and passive movement of the shoulder joint. The shoulder will be stiff and painful and occurs due to inflammation, fibrosis, scarring, and contraction of the capsule. A normal shoulder joint capsule is elastic and allows great range of motion. Inflammation and thickening of the shoulder capsule and may lead to adhesive capsulitis. Frozen shoulder may occur without any specific cause, however it may be triggered by a mild trauma to the shoulder.


This condition develops slowly and goes through three phases:

  1. Pain and freezing
  2. Stiffness or frozen
  3. Resolution

During the pain and freezing phase, the pain is worse at night and increases with any movement. This phase will last several months. During the second phase, range of motion is limited as pain is diminishing. This may last up to one year. The resolution phase may begin overtime and may last up to three years.


Conditions associated with frozen shoulder include:

  • Diabetes
  • Thyroid problems
  • Auto immune disease
  • Stroke
  • Rheumatoid arthritis
  • Trauma or post-surgery

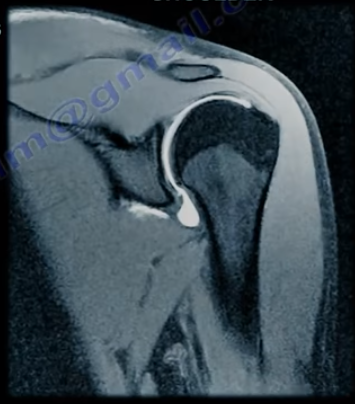
A patient with frozen shoulder will have loss of both active (movement without assistance) and passive (movement with assistance) motion. External rotation of the shoulder is very limited and the condition is self-limiting and may resolve on its own. X-rays are needed to rule out degenerative arthritis.  An MRI or arthrogram will show small fluid in joint cavity. Rotator cuff may be normal and synovitis and narrowing of the rotator cuff interval is usually seen.

Treatment consists of anti-inflammatory medications, physical therapy, injections, and manipulation under anesthesia. Surgery will be done in the form of a release of the capsule when nonoperative methods fail. The physician should always check the patient for diabetes.  

Tuesday, September 18, 2018

Ganglion Cyst of the Shoulder


Ganglion cysts can be important when they are located around the shoulder, especially when they are located in the suprascapular notch and the spinoglenoid notch. The suprascapular nerve passes under the transverse scapular ligament at the suprascapular notch. The transverse scapular artery runs above the transverse scapular ligament. The artery and nerve joint and then pass through the spinoglenoid notch under the inferior scapular ligament. The suprascapular nerve gives branches to the supraspinatus muscle and branches to the infraspinatus muscle.

Nerve compression from a ganglion cyst at the suprascapular notch affects both the supraspinatus and infraspinatus muscles, causing a decrease in abduction and loss of external rotation of the shoulder. Nerve compression at the spinoglenoid notch affects only infraspinatus muscle, causing loss of external rotation of the shoulder with the arm to the side. Spinoglenoid notch compression is usually associated with cysts and ganglia. In addition to compression of the suprascapular nerve, these patients may also have associated posterior labral tears.

Tuesday, September 11, 2018

Anatomy of the Posterior Cutaneous Nerve of the Thigh


The posterior cutaneous nerve of the thigh (small sciatic nerve) arises from the sacral plexus from S1-S3. The posterior cutaneous nerve of the thigh exits from the pelvis through the greater sciatic notch below the piriformis muscle. The nerve descends below the gluteus maximus muscle along with the inferior gluteal artery. It runs into the back of the thigh beneath the fascia lata and over the long head of the biceps femoris muscle to the back of the knee. The nerve then pierces the deep fascia and accompanies the short saphenous vein to the middle of the back of the leg. The posterior cutaneous nerve of the thigh innervates the distal part of the gluteal region, the skin of the perineum and the posterior part of the thigh.
The nerve can become compressed when passing through the tunnel below the piriformis muscle and under the gluteus maximus muscle. This may result in sensitivity disturbances of the innervation area of the nerve. Causes of the syndrome may be hypertrophy or abnormality of the piriformis muscle such as entrapment below the piriformis which compresses the nerve. Compression of the nerve can also occur due to prolonged sitting. During the clinical examination, pain and sensitivity will be evident. Pain and sensitivity disturbances are characteristic of the nerve distribution site in the posterior part of the thigh down the knee. This disturbance can be from hyperesthesia to hypoesthesia or burning sensation similar to meralgia paresthetica of the lateral cutaneous nerve of the thigh.

Differential diagnosis include piriformis syndrome. The patient should avoid sitting for long periods of time, especially on a hard base. Treatment consists of physical therapy, massage, and injection. Surgery is rarely needed.

Tuesday, September 4, 2018

SLAP Tear- Symptoms, Diagnosis, and Treatment


A SLAP tear is a tear that occurs where the biceps tendon inserts into the superior labrum. A SLAP tear is different from a Bankart lesion. SLAP tears are not common and can be hard to diagnose. Symptoms of a SLAP tear include: pain deep within the shoulder or in the back of the shoulder, as well as catching, popping, or clicking sensations. The patient may also experience pain when throwing a ball with a decrease in velocity and the feeling of having a dead arm after pitching. Patients will also experience pain with overhead activity which mimics impingement syndrome. This typically affects throwing athletes. When the biceps tendon is involved, pain may also be located at the front of the shoulder. A SLAP tear can be an isolated lesion or it can be associated with internal impingement, articular sided cuff tear, or instability.
A SLAP tear is diagnosed with a clinical examination and testing. The O’Brien’s test is the most commonly used test. Multiple tests are usually used including the anterior slide test and the clunk test. An MRI with contrast is the best imaging technique. When performing the O’Brien’s test, the patient is standing or sitting with the arm at 90° of flexion, 10° of adduction, and full internal rotation with the forearm pronated.  The examiner applies pressure to the forearm and instructs the patient to resist the applied downward force. Pain at the shoulder joint suggests a SLAP lesion. Decrease in pain of the shoulder joint on supination of the arm is suggestive of a SLAP tear.
Treatment consists of physical therapy, anti-inflammatory medications, injections, and surgery (when conservative treatment fails). If surgery is necessary, a labral debridement will be performed for minor tearing and fraying. Biceps Tenodesis is becoming popular, as it is a procedure that cuts the biceps tendon where it attaches to the labrum and reinserts it in another area, usually in front of the shoulder. A biceps tenotomy is a procedure that cuts the biceps tendon from the glenoid, releasing the long head of the biceps tendon from its attachment allowing it to fall into the upper arm out of the shoulder joint. A biceps tenotomy is probably best suitable for some elderly patients. A SLAP repair is a procedure which uses sutures to anchor the torn labrum to the glenoid. This repair is usually done for athletes and patients under the age of 40 years.

Tuesday, August 28, 2018

Massive Rotator Cuff Tear


To view my Youtube video, 'Massive Rotator Cuff Tear- Classic', click here.


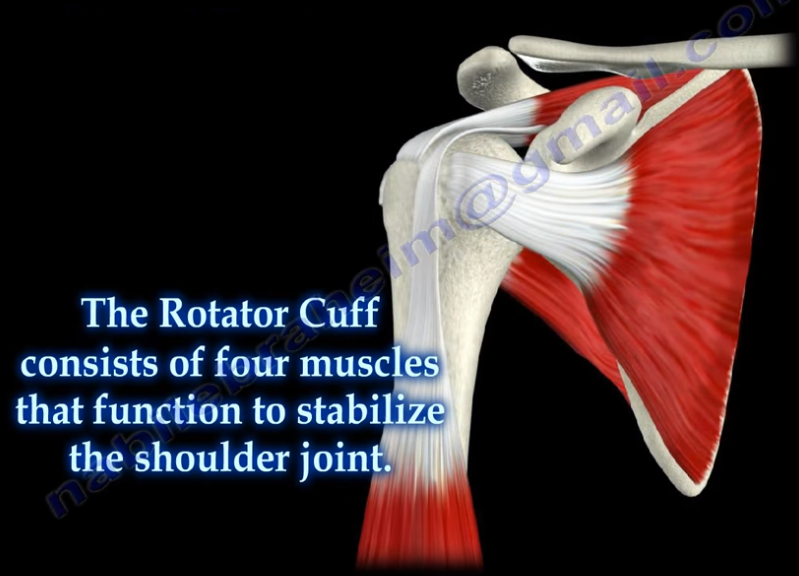
Massive rotator cuff tears are a disabling problem. These tears can cause pain, weakness, and sometimes swelling of the shoulder. The rotator cuff consists of four muscles that function to stabilize the shoulder joint: supraspinatus rotator cuff tendon, subscapularis tendon, infraspinatus rotator cuff tendon, and the teres minor rotator cuff tendon. The supraspinatus tendon is the most common of the rotator cuff tendons to become ruptured. Massive tears of the rotator cuff that are greater than 5cm usually involving both the supraspinatus and infraspinatus tendons.


Massive tears of the rotator cuff are defined as tears greater than 5cm, usually involving both the supraspinatus and infraspinatus tendons. Retraction of the rotator cuff tendons along with muscle atrophy and fatty infiltration can occur. This makes surgical reconstruction difficult with the surgical outcome being unpredictable and less than satisfactory.

Treatment varies from physiotherapy to replacement of the humeral head. Arthroscopic or open repair is usually the selected treatment. Reconstruction can be done in selected cases. A rotator cuff arthropathy is performed on massive cuff tears that are associated with superior migration of the humeral head as well as instability and arthritis of the shoulder. The patient will have pseudoparalysis and an x-ray will show shift of the humerus proximally. An MRI will show massive cuff tear with retraction at the level of the glenoid with atrophy of the muscle and fatty infiltration. A reverse shoulder is the treatment of choice for the elderly with rotator cuff arthropathy as it improves the pain and function. Hemiarthroplasty is the treatment for younger patients. A standard head or a big humeral head can be selected.


A patient with a massive tear of the cuff usually develops weakness of the shoulder and becomes unable to actively lift the arm without assistance. Fluid collection within the shoulder may occur with a massive tear of the rotator cuff.

Tuesday, August 21, 2018

Toe Deformities


Deformities of the toes are not uncommon and can occur from muscle imbalance, or other causes such as rheumatoid arthritis, diabetes, compartment syndrome, synovitis, or neurological disorders. Hammer toe occurs as flexion of the proximal interphalangeal (PIP) joint. Hammer toe is similar to the Boutonniere deformity of the finger. Claw Toe is a hyperextension deformity of the MTP joint and flexion of the PIP and DIP, resembling a pirate hook. Claw toe is similar to an intrinsic minus deformity of the hand, or “claw hand”. Mallet toe is similar in appearance to mallet finger, and is a flexion deformity of the DIP joint.

Tuesday, August 14, 2018

Triplane Fracture of the Distal Tibia


A triplane fracture of the distal tibia usually occurs during adolescence and occurs before complete closure of the distal tibial physis. The distal tibial physis (growth plate) is a weak area which closes from central to medial, with the lateral side being the last part to close. A Triplane fracture is a Salter-Harris Type IV Fracture, involving all three planes, the coronal (metaphysis), transverse (growth plate), and sagittal (epiphysis). The fracture has several variations and occurs due to external rotation forces. This fracture typically occurs in patients between 12-15 years of age.


Triplane fractures are complicated three-dimensional fractures. A two-part fracture is a Salter-Harris Type IV. A Three-part fracture is a combination of Salter-Harris Type III in an AP view and a Type II in a lateral view. CT scans are helpful.


An ORIF is necessary if there is displacement of the fragments of more than 2 mm.

Wednesday, August 8, 2018

Discoid Meniscus


The meniscus is a cushion structure made of cartilage which fits within the knee joint between the tibia and the femur. The medial meniscus is C-shaped and the lateral meniscus in the more circular. The meniscus is made up of type I collagen that provides shock absorption and stability to the knee joint. The meniscus helps to protect the knee joint, allowing the bones to slide freely on each other. Discoid meniscus is a rare variation of the meniscus that usually affects the lateral meniscus of the knee in less than 5% of the population and could be bilateral in about 25% of the cases.
Discoid meniscus is a large meniscus with abnormal attachment causing increased mobility of the meniscus. It causes a pop, click, or snapping with locking and pain. There will be loss of full knee extension with tenderness on the lateral joint space. Symptoms occur more during extension of the knee. The discoid meniscus occurs due to the abnormal development and increase in size of the meniscus. An x-ray could show increased widening of the joint space. An MRI will show the “bow tie” sign in three or more sagittal continuous cuts. The coronal MRI will show a thick and flat meniscus extending beyond the halfway point of the condyle.


Watanabe Classification of Discoid Lateral Meniscus


  • Type I: Block-shaped stable
  • Type II: Block-shaped, stable, partial meniscus (has good peripheral attachment)
  • Type III: Unstable meniscus with stability arising only form the ligament of Wrisberg. (no posterior meniscal tibial attachment).

Treatment


An asymptomatic patient will be treated with observation. A symptomatic patient may receive a partial meniscectomy and saucerization with repair of type III (no posterior tibial meniscal attachment)

Tuesday, July 31, 2018

Examination of the Acromioclavicular Joint


The acromioclavicular joint is located at the top of the shoulder, where the acromion of the scapula and the clavicle join together. The AC joint is a small synovial gliding joint that can be affected by arthritis and osteoarthritis. The oblique orientation of the joint’s articular surfaces may allow the acromion to be driven underneath the clavicle when the AC joint is injured. The condition could be subtle. Injuries of the acromioclavicular joint most commonly occur due to separation of the AC joint. Falling directly onto the shoulder can injure the ligaments that stabilize the AC joint. The AC ligament provides anterior-posterior stability of the AC joint. The posterior and superior AC ligaments are most important for stability. The coracoclavicular ligaments provide superior-inferior stability. Activity related pain with overhead activity and arm adduction.
During the physical examination, in order to test for injury to the AC joint, the physician will begin by palpating the AC joint. They should check to see if pain is present with direct palpation of the AC joint. If pressing down onto the AC joint causes pain, this is a sign of an AC joint problem such as distal clavicle osteolysis, arthritis, sprain of the AC ligament, or separation. Osteolysis of the distal clavicle is a localized area of inflammation, hyperemia, microfracture, bone resorption, and eventually arthritis of the AC joint. When pulling down on the shoulder, if there is a separation of the AC joint, the clavicle will rise and a bump will be seen in the area of the joint. Sometimes, this is demonstrated by adding weights and comparing both sides. The cross body adduction test can also be done by bringing the shoulder across the body. This squeezes the acromion and clavicle together, causing pain directly in the area of the joint if an AC joint separation or arthritis is present.

The acromioclavicular joint is best evaluated using the Zanca view radiograph. Using the Zanca view, the x-ray beam is directed with a cephalad angle of 15 degrees. Clavicular osteolysis can be assessed using the Zanca view. The acromion will be normal with the abnormality isolated to the distal clavicle. The Zanca view is also used for diagnosis of arthritis of the AC joint. It can show osteophytes and joint space narrowing. The patient’s symptoms may not correlate with the x-ray findings. An MRI will show an increased signal and edema in the AC joint.

Tuesday, July 24, 2018

Lumbosacral Plexus


The sciatic nerve is the key nerve of the lumbosacral plexus. It arises from the spinal nerves of L4 through S3. The sciatic nerve is the cornerstone of the lumbosacral plexus. Knowledge of the lumbosacral plexus starts with the sciatic nerve because it is the most important nerve. The lumbosacral plexus is comprised of the sciatic nerve and S4. The branches of the lumbosacral plexus are the superior gluteal nerve (L4-S1), the inferior gluteal nerve (L5-S2), the posterior cutaneous nerve of the thigh (S1-S3), and the pudendal nerve (S2-S4) (SIPP).