Showing posts with label Orthopaedic Emergencies. Show all posts

Monday, August 12, 2019

Open Fractures of the Tibia


Open Fractures of the Tibia

25% of tibial shaft fractures can be open. Open fractures can lead to complications including wound problems, osteomyelitis, nonunions, and infected nonunions. The treatment of open fractures of the tibia can be challenging. A lot of the concepts are not black and white; they may be in the grey zone. We don’t know the best time for debridement. We don’t know what the optimal irrigation solution is and what the optimal pressure for the fluid is. We don’t know for sure the ideal duration of giving antibiotic prophylaxis, but we know that it is important to give the appropriate antibiotics early and do meticulous debridement. We know that the IM rod is better than the plate fixation or external fixator, and the result of the reamed IM rod or unreamed IM rod is the same. We need to close or cover the wound before 1 week and the vac can be used provisionally when we cannot close the wound, primarily at the optimal time. A grade I fracture is less than 1 cm. a grade II fracture is 1-10cm. A grade III fracture is more than 10 cm, and there is contamination. Grade III fractures are divided into three types. Grade IIIa fractures require adequate tissue for closure (or skin graft). Grade IIIb fractures require extensive periosteal stripping and the patient will need a flap (rotational or free flap). Grade IIIc fractures have a vascular injury that requires repair or amputation. The relative indication for amputation is warm ischemia for more than 6 hours, absent plantar sensation and severe ipsilateral foot trauma.
The most predictive factor for amputation is the severity of the soft tissue injury in the ipsilateral extremity. When comparing limb salvage versus amputation, the patient’s outcome is generally the same at 1-5 years. Lack of plantar sensation does not predict poor outcome after limb salvage. Segmental fractures are Grade III fractures, even if the open fracture is 1 cm. The ideal irrigation solution and the pressure used to controversial. Timing of the initial debridement is controversial. Irrigation and debridement within 6 hours was the gold standard in the past. Debridement is performed as a priority procedure no later than the morning after admission. There is no difference in infection rate for a patient who has the initial surgery before or after 6 hours, including patients with Type III open fractures. More than 40% of the patients usually wait longer than 6 hours for their initial surgery after arrival at the hospital. Delayed surgery for less severe fractures is acceptable as long as the debridement is done as a priority the following day. Unless there is a gross contamination, evidence is not clear as to when is the best time for the debridement. It seems like giving the patient antibiotics promptly is more important than the time of debridement. The preferred solution is normal saline and low pressure irrigation. Low pressure lavage may reduce reoperation rates due to infection, nonunions, and wound healing problems. Normally the tradition is to use 3, 6, and 9 liters of solution for Type I, Type II, and Type III open fractures (just recommendations). There is increased risk of wound healing with antibiotic solution. Meticulous irrigation and debridement of open fractures is important in decreasing the infection risk. Prophylaxis should be started as soon as possible. All patients with open fractures should receive first generation Cephalosporin’s that will cover gram-positive bacteria. You can give penicillin for farm injuries and clostridia prone wounds. You will give clindamycin if there is a penicillin allergy. In Type III open fractures, add aminoglycoside, such as gentamicin. It was found that local antibiotics delivery at the site of injury decreased the infection risk, such as cement beaded loaded with antibiotics. Antibiotic should be given within 3 hours of the time of injury (preferably given as soon as possible). There is reduction of 59% of acute infection in patients with open fractures treated with antibiotics. The infection rate is 1.6 times greater if antibiotics are given after 3 hours. Type I and Type II open fractures require antibiotic coverage for 24 hours after wound closure. For Type III open fractures, antibiotic administration should be given for a period of 72 hours after the injury and no more than 24 hours after wound closure. After the initial debridement, the patient will need staged debridement within 24-48 hours. There is a reduction infection rate, acute and chronic, for Type III open fractures with the use of systemic antibiotics and aminoglycoside cement beads compared with antibiotics alone. This combination of antibiotics lowers the infection rate for any open tibial fracture that is treated with an IM rod. Its affect is more noticed in Type III injuries. Plating of open fractures may cause chronic infection and infected nonunion. The healing time is doubled with plated open fractures. The IM rod resulted in a better alignment and lower reoperation rate than using external fixator. Also, no difference in the infection rate between the IM rod and the external fixator. You can use a reamed nail or an unreamed nail. They both have a comparable result and no difference in the outcome.
When reaming, you can use a bigger rod that provides better stability. Reamed nailing is superior in closed tibial fractures, but it is not superior in open tibial fractures. Reaming can cause increased pressure and disruption of the endosteal blood supply, can cause thermal necrosis and fat embolism with increased intramedullary risk of infection. The unreamed rod uses smaller nails and results in less stability but preserves the endosteal blood supply. Unreamed IM tibial rod appears to have a shorter time to union and fewer incidence of knee contractures when compared with circular wire external fixator. Nowadays, more and more orthopedic surgeons are using reamed nails for open fractures of the tibia. If you have a spiral fracture of the distal 1/3 of the tibia, you will need to get a CT scan of the ankle to identify a posterior malleolar fracture, which should be fixed before insertion of the IM rod. There is a lack of evidence to support the value of external fixator over the IM rod in open factures of the tibia. Due to patient discomfort, the high incidence of pin tract infection and loss of alignment, external fixator should not be used as a definitive fixation. Use external fixator temporarily (less than 4 weeks) and replace it with a rod in about 14 days. External fixator may be utilized for severely contaminated open fractures. Tibial fractures treated with a shorter duration of external fixator has reduction of the infection risk by 80%. When there is a shorter interval between removal of the external fixator and insertion of the IM rod of the tibia, there is a reduction of the risk of infection by 85%. In less severe soft tissue injuries, you do primary closure without tension. In cases of delayed closure, soft tissue coverage should be done within 7 days. Soft tissue coverage beyond 7 days will increase the infection. There is no difference in the incidence of infection in patients who had primary closure and delayed closure of the wound. It is recommended to do primary closure for Type I, Type II, and Type IIIa fractures with tension free closure and after timely antibiotic prophylaxis and adequate debridement. Intraoperative culture after debridement has no value. It does not predict future infection. In the upper 1/3 of the tibia, you can treat it by a medial gastrocnemius flap. In the middle 1/3 of the tibia, you can treat it by a soleus rotational flap. The use of a free flap for soft tissue coverage was less likely to have wound complications than the use of a rotational flap. The zone of injury may be larger than expected, and it may include the rotated muscle flap. The negative pressure wound therapy (the vac) is used frequently. The vac provides provisional coverage for wounds where the physician cannot do primary closure. There is decreased infection rate when using the vac. The vac is used for coverage after the initial debridement of the open fracture until the definitive coverage is done. It is a good temporizing dressing and can also be used in fasciotomy wounds. The vac promotes local wound healing. Bone morphogenetic protein (BMP2) decreases the need for secondary surgery and is used in acute open tibial fractures treated with IM rod.

Tuesday, July 17, 2018

Intra-articular Extensile Approach for Tibial Plateau Fractures


Several types of tibial plateau fractures are a complex management problem. The knee joint may have a significant comminution and depression, and the physician may need to take an extensile approach for reduction and fixation of this fracture. Personally, I use the intra-articular extensile approach for tibial plateau fracture reduction and fixation. In general, fracture of the tibial plateau is a complicated problem.


A vascular evaluation is necessary. The ankle-brachial index (ABI) is needed in some types, such as in medial plateau fractures or in severe types, such as Schatzker Type V or Type VI. The ABI should be more than 0.9. Usually, medial tibial plateau fractures are considered to be a knee dislocation. A fasciotomy may be needed if compartment syndrome occurs. The soft tissue condition may be bad, and an external fixator may be initially used until the soft tissue condition improves.

The association between tibial plateau fractures and meniscal tear is not uncommon. A lateral plateau fracture will create a lateral meniscal tear, while the medial plateau fracture will cause a medial meniscal tear. A tear of the meniscus is usually peripheral. It should be recognized and dealt with. The physician may want to look at the x-ray and see if there is a depression or separation of more than 6mm, as this indicates a high chance of meniscal tear.

The posteromedial fragment is another problem with tibial plateau fractures which needs to be fixed separately. When an extensive comminuted displaced tibial plateau fracture occurs, the physician may need excellent exposure of the articular surface to allow for anatomic reduction of the joint and visualization and repair or debridement of the meniscus if it is torn. This extensile exposure is important, especially if the posterior part of the plateau is involved. The traditional way to see the articular cartilage of the tibial plateau is to use the submeniscal approach by cutting the coronary ligament, but the exposure is limited. Other extensile approaches are also developed; however, we use the extensile intra-articular approach for complex, comminuted tibial plateau fractures. This involves anterior detachment and retraction of the meniscus to improve visualization of the tibial articular surface. This approach can be utilized for lateral or medial tibial plateau fractures and it is especially helpful in diagnosing and repairing the torn meniscus. This allows for inspection of the meniscus pathology in fractures of the articular surface. This improves reduction of the fracture and the torn meniscus is repaired and reattached to the coronary ligament. Incision and reflection of the meniscus allows great exposure and inspection of the joint which is followed by reattachment and suturing of the anterior horn of the meniscus to its normal position which is followed by reattachment of the meniscotibial (coronary) ligament. The sutures are tied to the sides of the patellar tendon on the opposite side of the meniscus.

Tuesday, April 3, 2018

Cauda Equina—Central Disc Herniation


Disc herniations usually occurs posterolaterally, but it may also be central. The cauda equina is composed of several nerves within the lower end of the spinal canal. The top of the spinal cord is a tubular bundle of nervous tissue extending from the brain.

The following section of the spinal cord is called the Conus Medullaris and is the lower end of the spinal cord. The Cauda Equina is made up of multiple nerve roots beginning at the level of L1.


The most common disc herniation is the Posterolateral Disc Herniation. This type of herniation is a nerve root injury, which will cause changes to both the sensory and motor skills as well as the reflexes. A posterolateral disc herniation usually affects the foot and ankle, and may cause unilateral leg pain and weakness. Observe for a positive straight leg raising test. These herniations are usually initially treated with conservative methods.  


A central disc herniation will cause cauda equina syndrome, which is a compression over the lumbosacral nerve roots. This compression will cause more back pain than leg pain, and bladder and bowel symptoms will be evident. This herniation is considered a surgical emergency.

Tuesday, February 20, 2018

Jefferson Fractures


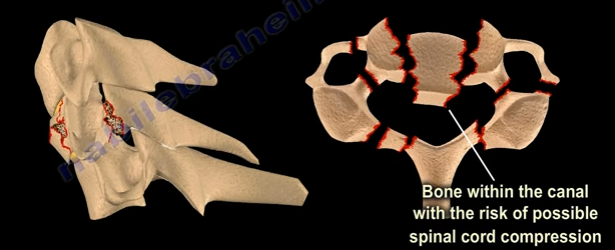
Fifty percent of patients with Jefferson fractures will have associated spine injuries. The canal is wide with a low risk of spinal cord injuries unless the transverse ligament is disrupted. It is difficult to view Jefferson Fractures on an x-ray (usually seen on the lateral side”. This fracture is considered a “Junctional Fracture” and could be missed. The classic Jefferson fracture is a burst fracture that results from an axial load. It could be a four part fracture with bilateral fractures of the anterior and posterior arch. There are variations which include two and three part fractures and incomplete formations of the posterior arch can be mistaken as a fracture.
When speaking of Jefferson fractures, it is important to be familiar with the structures that may be involved. These bony structures include: The Atlas (C1), Axis (C2), and the odontoid process. C1 and C2 are stabilized together by the transverse ligament and C1 and C2 provide a 50% of rotation of the neck. The C1 is a ring. At the upper cervical region, the spinal canal is 2.5 times larger than the cord size. The stability and treatment of Jefferson fractures depends on the integrity of the transverse ligament and the displacement of the fracture. You need to know about the important ligaments related to the Jefferson fracture. These ligaments include: the transverse ligament, the apical ligament, and the Alar ligament.

Diagnosing ligamentous injury


In order to determine a ligamentous injury, the physician will want to check the Atlanto-dens interval (A.D.I). Normally, this interval should be less than 3mm in adults and less than 5mm in children. If the ADI is between 3-5mm, this indicates an injury to the transverse ligament; the transverse ligament holds the odontoid and C1 together, alar and apical ligaments will be intact. If the A.D.I measures greater than 5mm, then there is an injury to the transverse, alar, and apical ligaments.


Fracture Types


A bony injury with the intact transverse ligament and a lateral mass displacement less than 7mm and the A.D.I is less than 3mm is considered a stable fracture. Nondisplaced fractures of this nature should be treated with a rigid orthosis. If the fracture is displaced, a halo will need to be used.
Another type of fracture can occur at C1 with a transverse ligament tear. The Atlanto-dens interval will be more than 3 mm in adults. The treatment will depend on the type of injury to the transverse ligament. With bony avulsions of the transverse ligament, the halo will need to be used cautiously. However, some surgeons prefer to do a fusion of C1 and C2. If there is an intrasubstance tear of the transverse ligament, the surgeon will perform a fusion at C1-C2. The surgeon will need to do early surgery as this is a significant injury with a risk of spinal cord compression.


In regards to “Open Mouth Views”, the normal overhang is visible during an “Open Mouth View”. If it is just a bony injury Jefferson fracture, the combined overhang will be less than 7mm and the transverse ligament is intact and it is a stable fracture. If a Jefferson fracture has a combined overhang of more than 7mm, then the transverse ligament is probably torn and there is an unstable fracture present.

Radiological Studies


A CT scan is probably the best study in diagnosing the characteristics of the bony injury. An MRI is the best study in diagnosing any associated transverse ligament injuries.

Tuesday, January 30, 2018

Hip Dislocations


Hip dislocations can occur posteriorly or anteriorly; however, any type of hip dislocation is considered an emergency.


Posterior hip dislocations are more common and the lower limb will be flexed, adducted, and internally rotated. Posterior dislocations are frequently caused by dashboard injuries. The impact with the car dashboard drives the femoral head backwards out of the acetabulum. The physician will want to observe sciatic nerve function and examine the knee to rule out a PCL injury as well. Weakness of the ankle and toe dorsiflexion due to an injury to the peroneal division of the sciatic nerve may result in foot drop. The patient will also be unable to dorsiflex the ankle.
Anterior hip dislocation is rare. Superior Anterior hip dislocation results from the lower limb being extended, abducted, and externally rotated. Inferior Anterior Hip Dislocations (obturator type) results from the lower limb being flexed, abducted, and externally rotated.

An emergency reduction of dislocations is needed in less than 8 hours of the injury. An urgent reduction is mandatory to avoid avascular necrosis and interruption of the blood supply, which leads to a collapse of the femoral head. AVN is the death of a segment of bone.


Treatment


A CT scan should be obtained after reduction to evaluate the presence of fragments in the joint and access stability of the joint. Hip joint dislocations may be associated with acetabular or femoral head fractures (Pipkin). An urgent closed reduction of the hip dislocation followed by stabilization of either of the fractures if needed according to the protocols.  

Tuesday, December 5, 2017

Pelvic Fractures with Bleeding


Pelvic fractures may cause significant bleeding. The superior gluteal artery is responsible for the majority of bleeding in pelvic fractures with an arterial injury. Most of the bleeding in pelvic fractures is from the veins and the fracture itself. Hemorrhage is the most life-threatening complication associated with pelvic injuries and will typically occur at the Superior Gluteal Artery. Hemorrhage of the Superior Gluteal Artery can be fatal. Approximately 10% of patients will have severe bleeding. Severe bleeding usually occurs in fracture patterns that are highly unstable to both rotational and vertical forces.


APC III (open book like type) is the complete disruption of anterior SI, sacrotuberous, and sacrospinous ligaments; disrupted posterior SI ligaments.
Vertical Shear Fractures are very bad fractures as they cause the complete disruption of the anterior and posterior ligaments; cephaloposterior displacement. Anteroposterior compression or vertical shear injuries are consistently associated with a higher risk of mortality from bleeding. The mortality rate is directly related to the amount of shock the patient is in at the time of presentation.
When treating patients with pelvic fractures and massive bleeding, it is important to remember that the patient will lose approximately 35% of their blood volume with acute hemorrhage before a sustained decrease in systolic blood pressure occurs. Immediate application of a pneumatic anti-shock garment is absolutely contraindicated in patients with a rupture of the diaphragm. Ringer’s lactate is the preferred initial fluid replacement used to resuscitate hypovolemic trauma patients in shock. A hypotensive blunt trauma patient will be given an initial fluid push with 2,000mL of Ringer’s lactate. A patient with bleeding and in shock will probably require O negative blood. If the patient is given 4 units of blood but remains hemodynamically unstable, then angiography and embolization is needed. Immediate application of an external fixator is another method to control bleeding, especially if the pelvis is unstable in external rotation. An abdominal and pelvic CT scan will clearly define the bony injury as well as the extent and source of the bleeding.
The best treatment for pelvic fractures with bleeding is a blood transfusion with correction of hypothermia and coagulopathy.      

Monday, November 6, 2017

Bulbocavernosus Reflex and Spinal Shock


The bulbocavernosus reflex indicates the absence or presence of spinal shock. Spinal shock usually occurs between 24-72 hours after a spinal injury. Spinal shock is manifested by the absence of the bulbocavernosus reflex, hypotension, bradycardia, and complete loss of motor sensation and reflexes. When the reflex is absent, this means that the patient is in spinal shock because the anal sphincter will not contract when the reflex is absent.

When the reflex is present, this signals the end of spinal shock; the anal sphincter will contract when the reflex is present. The reflex is check by monitoring anal sphincter contraction in response to squeezing of the penis of clitoris, or by pulling on an indwelling Foley catheter. It is a polysynaptic response mediated by S2-S4.

What is Spinal Shock?

Spinal shock is the loss of sensation and motor power following a spinal cord injury. Spinal shock is the loss of sensation and motor power following a spinal cord injury. After an injury to the spine, if the patient has no motor or sensory below the level of the lesion, the physician must determine if the patient is in spinal shock by checking the bulbocavernosus reflex.
If there is no anal contraction (absent bulbocavernosus reflex), this indicates that the patient is still in shock and the prognosis cannot be determined. If anal contraction is present (positive bulbocavernosis reflex), this indicates the end of spinal shock. The patient’s condition and prognosis at this point can be determined by examining sacral sparing (positive sacral sparing indicates an incomplete lesion).

Loss of sensation and motor power below the level of injury indicates complete spinal cord injury. Once the diagnosis of neurogenic shock is established, the blood pressure should be managed with vasopressors to prevent fluid overload. With the end of spinal shock, the prognosis can be determined. Examine the patient thoroughly, including sacral sparing. The patient may have normal, partial, or complete indications. 

Tuesday, October 31, 2017

Platelet Rich Plasma Therapy


Platelet Rich Plasma, or PRP, is a volume of the plasma of autologous blood having a platelet concentration above the baseline. Platelets facilitate healing by stimulating the release of different growth factors. The growth factors recruit stem cells that assist with healing, repair, or regeneration of the injured tissue. PRP is injected directly into the injured tissue, stimulating a healing response in a more powerful form.
Red Blood Cell
In order to understand PRP, you must know that platelets are components of blood cells. The development of PRP focuses on the concentration of the patient’s own blood platelets to create an active mixture of growth factors. The other components of blood are the red and white blood cells. Red blood cells carry oxygen from the lungs and deliver it to the body tissues. White blood cells form our immune system and help the body to fight against infection and foreign materials.


Active Platelet
Platelets aid in hemostasis (stop the bleeding) and in building new tissues—they act as a scaffold for tissue regeneration. Platelets aid in the attraction and binding of stem cells. Platelets act as the directors while stem cells work. Platelets divide, multiply and differentiate to become the healing cells for injured tissue. The platelets become activated by thrombin and other factors which cause a change in their morphology and the release of multiple growth factors. These growth factors bind themselves to the receptors of the cell causing intracellular changes down to the nucleus and affecting its DNA.  The result is a change in the performance and function of the cell.
In order to produce PRP, 30-60mLs of the patient’s own venous blood is drawn from the antecubital vein. The blood is then placed into a device to be centrifuged which separates the blood into platelet poor plasma (PPP), red blood cells (RBC), and platelet rich plasma (PRP). The blood is then placed in a centrifuge for 15 minutes at 3,200 rpm. The centrifuge spins and separates the platelets from the rest of the blood components and increases the concentration of platelets and growth factors. The more platelet concentration, the greater the healing power. After the centrifuge process is complete, the plasma has been separated from the blood producing the PRP and the platelet poor plasma is withdrawn to be discarded. Platelet rich plasma is withdrawn for injection. Sodium Bicarbonate is used to neutralize the acidity of the sample. The more platelet concentration, the more growth factors and healing power the sample has.
Ultrasounds help deliver a concentrated sample of platelets to the injured tissue. Ultrasound increases the accuracy of delivering the sample to the injured tissue. Preferably, injections should be performed with the aid of ultrasound imaging. Needling induced injury releases thrombin which activates the platelets. Platelets help in hemostasis and produce growth factors as well as chemotactic factors. Platelets act as a scaffold for mesenchymal stem cells which start the process of tissue regeneration. Patients will typically experience minimal to moderate discomfort which may last up to one week following the injection. Avoid the use of anti-inflammatory medications for 6 weeks after the injection.

Tuesday, October 24, 2017

Hangman's Fracture


The hangman’s fracture refers to the bilateral fracture of the pars interarticularis. When this fracture occurs, the spinal canal is widened and there is a low risk for spinal cord injury. This fracture usually occurs due to motor vehicle accidents.

Hyperextension will fracture the pars interarticularis with secondary flexion, injuring the disc and posterior ligament. The patient may have other associated spine fractures.


Hangman’s fractures are identified by types using the Levine and Edwards Classification.
Type I


Type I:


  • Stable fracture with less than 3mm displacement
  • No angulation
  • Treatment: Cervical Orthosis
Type II

Type II:

  • Most common type
  • Significant translation and some angulation
  • Unstable fracture
  • Treatment: Cervical traction to improve the displacement and immobilization in halo vest
Type IIa

Type IIa:

  • Slight translation but severe anglulation seen in flexion distraction injuries with tearing of the posterior longitudinal ligament and the disc.
  • The fracture is unstable
  • Treatment: reduction in extension and compression in a halo
  • Do NOT use traction when there is severe angulation of the fracture  

 
Type III

Type III:

  • C2-C3 facet dislocation
  • Rare fracture that results from initial anterior facet dislocation of C2 on C3, followed by an extension injury fracturing the neural arch.
  • Results in translation with unilateral or bilateral facet dislocation of C2-C3.
  • Unstable fracture
  • Treatment: surgery for reduction of the facet dislocation and stabilization of the injury
 

Typical and Atypical fractures

A typical hangman’s fracture displaces the vertebral body anteriorly and its posterior element posteriorly. This creates increased space for the spinal cord.

Atypical Hangman's Fracture
An atypical hangman’s fracture line leave the canal circumferentially intact, which puts the spinal cord at risk of injury if displacement occurs.


Tuesday, September 19, 2017

Lactic Acid and Base Deficit in Trauma Patients


Lactic acid is a byproduct of anaerobic metabolism (Metabolism without oxygen). Normally, the cells use anaerobic metabolism and it breaks down the glucose to form energy. Normally, the cells use oxygen available to breakdown the glucose and produce ATP. This occurs when you have oxygen. If the body does not have the oxygen, it then converts the metabolism to an anaerobic metabolism. The end product is lactic acid. If the body is acidic, and the pH drops, this means that there is a tissue ischemia. If we take the glucose (CCCCCC), and break it down, you will have two pyruvates—each attached to a CCC. That’s not a lot of energy and the pyruvate is a mild acid.

There are different ways to get more energy, such as going to the mitochondria to use the oxygen and produce more ATP. When we break down the glucose to produce energy in the presence of oxygen, so the glucose will split into two separate three carbon molecules called the pyruvate and produces ATP. If you don’t have oxygen, then the pyruvate will be attached to hydrogen atoms, which is H+ (proton that is an acid). If you are acidotic and a sick patient, you will have a lot of floating hydrogen atoms and a lot of floating protons.

The pyruvate will attach to the free hydrogen protons. The H+ pyruvate is called lactic acid. It is a pyruvate that is holding onto hydrogen. The lactic acid is the end product of anaerobic metabolism.

Now, with a base deficit, as the number of protons goes up, which is hydrogen, then the pH will go down and the patient will become acidotic. The body uses bicarbonate as a buffer if the pH goes down. There are a lot of protons within the body and the bicarbonate will be exhausted in this situation. The bicarbonate goes down because we are combining it with the protons. When the bicarbonate goes down, this becomes metabolic acidosis.

When you combine the bicarbonate with the protons, this will make carbonic acid (H2CO3), rather than HCO3-, which is bicarbonate. The carbonic acid can give water (H2O), and CO2. The lactic acid will give out the protons and be buffered by the bicarbonate, leaving lactic acid. When this occurs, the bicarbonate will go down, and this will be the base deficit.

When checking if a patient has been resuscitated, you can check in several ways

The two ways this is asked on exams:
  1. Base deficit from -2 to +2
  2. Serum lactate level (normal is less than 2.5, some sources use normal less than 2)

Friday, September 8, 2017

Orthopaedic Emergencies Part IV


In our final blog post regarding Orthopaedic Emergencies, we will review:

  1. Transverse Atlantal Ligament Rupture
  2. Bilateral Cervical Facet Dislocation
  3. Spinal Cord Compression
  4. Cauda Equina Syndrome


Transverse Atlantal Ligament Rupture


The normal Atlanto-Dental Interval is less than 3mm. An A.D.I measuring greater than 3mm will be translationally unstable in the sagittal plane due to transverse atlantal ligament rupture. This is usually apparent on x-rays or CT scan. If the condition is not diagnosed, it can result in spinal cord compression, respiratory arrest, and a catastrophic outcome. Treatment typically requires a posterior atlanto-axial arthrodesis.


Bilateral Cervical Facet Dislocation


Facet dislocations of the cervical spine:

  1. Unilateral Facet Dislocation
    1. Displacement is less than 50% of the vertebral body width
    2. May need surgery
  2. Bilateral Facet Dislocation
    1. Displacement greater than 50% of the vertebral body width
    2. Usually needs surgery
    3. Exclude disc herniation

Obtain a preoperative MRI to rule our disc herniation associated with facet dislocations.


Spinal Cord Compression


Spinal cord compression is more common with cervical spine injuries and thoracic spine injuries. Neurogenic shock resulting from spinal cord injury may complicate resuscitation of the patient and should be differentiated from hypovolemic shock. It is important to look for hypotension and bradycardia as well as thoracolumbar fractures which could be missed. Treatment consists of emergency management involving resuscitation and hemodynamic stabilization with concurrent neurologic examination. Protocol requires steroids given early. Definitive treatment consists of stabilization of unstable spinal injuries.


Cauda Equina Syndrome


Central disc herniation compressing the cauda equine. It results from injury to the lumbosacral nerve roots within the spinal canal. This syndrome presents with involvement of the bladder, bowel, and lower limbs and usually results from central disc herniation or fractures. Central disc herniation or bony fragments results in the compression of the nerve roots. Early diagnosis is imperative to find the cause of the compression on the nerve roots. Urgent decompression by the removal of the central disc herniation or stabilization of the fracture is necessary for treatment.

Friday, August 25, 2017

Supracondylar Fracture Humerus & Circulation


The neurovascular status must be examined in patients with supracondylar fractures. Avoid treating the patient with a cast that may cause hyperflexion of the elbow. Bending the elbow too much may affect the brachial artery. It may not be acceptable to reduce the fracture at 90° of elbow flexion. In these cases, choose a different alternative to casting, such as pinning (closed or open technique).
It is important to remember that Volkmann’s ischemic contracture may occur due to injury to the brachial artery. You have to make sure that you restore the circulation.


A few scenarios to go over
1.       The Patient has good circulation with no radial pulse (hand perfused)

a.    In this case, you would do a closed reduction and pinning as well as in-patient monitoring for 24-48 hours in order to assess the circulation of the extremity

2.       Cold Cyanotic Hand (no perfusion or you may have underperfusion)
a.       This may occur before or after attempting reduction
b.      The patient must immediately go to the operating room for closed or open reduction and pinning (No matter if the hand is underperfused or perfused at all)
c.       Monitor the circulation for anticipation of improvement
d.      If there is no immediate improvement, explore the antecubital fossa in order to explore the brachial artery
e.      Have the help of a vascular surgeon
f.        Assess the circulation

You want to think of this scenario like a knee dislocation. If you have pulses or no pulses with a knee dislocation, then you reduce the knee dislocation. It is the same with supracondylar fractures: pulses or no pulses, pink or not pink hand, cold cyanotic hand—do closed reduction and pinning. It is a more urgent condition if there are perfusion problems.


3.       Perfusion Disappears During Reduction or Monitoring
a.       If the perfusion gets worse after reduction of the fracture, then you need to find out what has happened.
b.      You will need to perform an open exploration and without an arteriogram

4.       Circulation Disappears After Closed Reduction and Pinning
a.       Reduction caused harm to the patient
b.      The pins need to be removed, the fracture needs to be unreduced and check the circulation.

c.       Check to make sure that the neurovascular bundle does not become trapped in the fracture gap after closed reduction and pinning. 

Tuesday, August 22, 2017

Orthopaedic Emergencies Part III


Open Fractures


Open fractures are categorized with the Gustilo-Anderson Classification. A Grade I Injury indicated a clean wound, less than one centimeter long with minimal injuries to the soft tissue and minimal bone comminution. A Grade II injury consists of a moderately contaminated wound greater than one centimeter long with moderate tissue injury and moderate bone comminution. A highly contaminated wound, usually greater than ten centimeters, segmental fractures, farm yard injuries, high velocity gunshot wounds and fractures occurring in a highly contaminated environment regardless of the size of the wound.
Grade III injuries are classified further into A, B, and C. Grade III A is a severe soft tissue injury with a crushing comminuted fracture; soft tissue coverage of bone possible. Grade IIIB consists of a very severe loss of soft tissue cover with poor bone coverage and variable—may be moderate to severe bone comminution. Grade IIIB usually requires a soft tissue reconstructive surgery in the form of local or distant flaps. Grade IIIC fractures consists of a vascular injury requiring repair or amputation. There is a very severe loss of soft tissue cover with moderate to severe bone comminution. Injury of the femoral artery from the posteriorly displaced proximal fragment of a Grade III C open supracondylar fracture of the femur. Grade III C has a high rate of amputation, nonunion and infection.

Hip Infection (Septic Arthritis)

An infection in the hip is a serious disease especially in children. The intraarticular structures will be inflamed and the increased intracapsular pressure will decrease the blood supply to the femoral head. Infection is associated with a high risk of avascular necrosis. The position of the limb in the stage of effusion, flexion, abduction, and external rotation. Complications are severe and much more common in children. Complications include: pathological dislocation, avascular necrosis, osteomyelitis, and pelvic abscesses. Urgent aspiration followed by drainage of the hip joint combined with intravenous antibiotics are the typical treatment for hip infections.  

Necrotizing Fasciitis


Necrotizing Fasciitis is an insidiously advancing soft tissue infection characterized by widespread tissue necrosis. The most common causative organism—group A beta—hemolytic streptococcus. There is a high mortality rate with sepsis and renal failure. Amputation and the mortality rate is increased due to a delay in diagnosis. Predisposing factors for necrotizing fasciitis include: trauma, surgery, as well we urogenital and anogenital infections. There are three types of necrotizing fasciitis: Type I—which is Polymicrobial, Type II—which is a Group A beta-hemolytic streptococcus, and Type III—which is gas gangrene-clostridial myonecrosis. Treatment consists of an immediate surgical debridement combined with intravenous antibiotics and hyperbaric oxygen if necessary.

Fracture with Soft Tissue Compromise

Soft tissue compromise associated with fracture blisters, ecchymosis, and severe bruising which indicate a greater degree of deep soft tissue damage. Blood filled fracture blisters are associated with high wound complications. Initial management involves application of a spanning external fixator with the fracture dislocation held in reduction with traction. The definitive management involves replacing the spanning external fixation with a hybrid fixator or plate once the soft tissue edema is resolved and the skin is wrinkled, usually in one to three weeks. Spanning external fixation can often be combined with percutaneous fixation of large articular fragments. A soft tissue compromise is more common with tibial plateau fractures and tibial pilon fractures with diaphyseal extension. A calcaneal avulsion fracture is considered an emergency. Urgent reduction and fixation is mandatory to avoid soft tissue complications. Type I—is a “sleeve” type tuberosity fracture. This pressure will create skin necrosis and significant soft tissue complication.


Stay tuned for Orthopaedic Emergencies Part IV!